
|
시장보고서
상품코드
2123351
비침습적 산전 검사 시장 : 점유율 분석, 업계 동향과 통계, 성장 예측(2026-2031년)Non-Invasive Prenatal Testing - Market Share Analysis, Industry Trends & Statistics, Growth Forecasts (2026 - 2031) |
||||||
 Mordor Intelligence
에 의하면, 비침습적 산전 검사 시장 규모는 2025년 39억 달러, 2026년 44억 3,000만 달러에서 2031년까지 83억 6,000만 달러로 확대되어 2026년부터 2031년까지 CAGR 13.53%를 나타낼 것으로 예측됩니다.
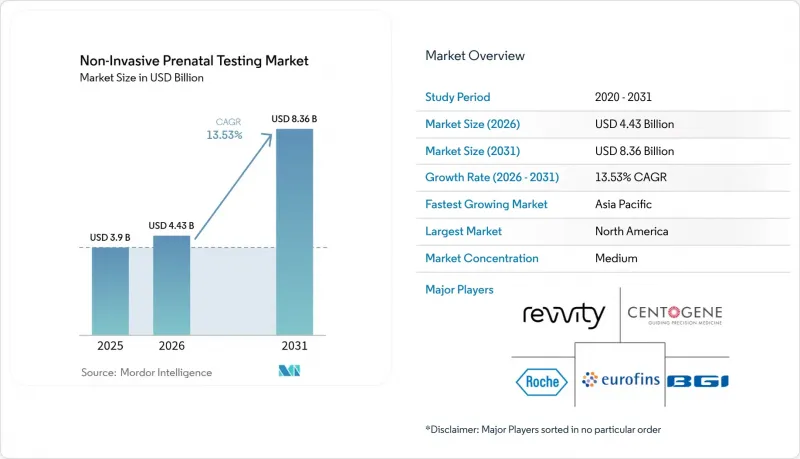
본 보고서는 기술(차세대 염기서열 분석 등), 검사 유형(수적 이상 스크리닝 등), 임신 주수(10-12주 등), 검체 유형(모체 혈장 유래 cfDNA 등),구성 요소(장비 등), 최종 사용자(병원 등), 유통 채널, 용도 및 지역별로 분류되어 있습니다. 시장 예측은 금액(달러) 기준으로 제시되어 있습니다.
전 세계 비침습적 산전 검사 시장 동향 및 인사이트
전 세계 임산부의 고령화로 인해 염색체 수 이상 위험이 높아지고 있습니다.
여성들은 경제적 및 경력상의 이유로 출산을 늦추고 있으며, 모든 OECD 회원국에서 임산부 연령의 중앙값이 상승하고 있습니다. 미국에서는 2024년에 첫 출산 시 평균 연령이 27.8세에 달했습니다. 노화에 따른 삼염색체증 발생률 증가로 인해 산부인과 의사들은 cfDNA 선별 검사를 보편적으로 권장하고 있습니다. 특히 35세 이상 여성을 대상으로 한 검사에 대해 공공 프로그램이 지원금을 지급하는 지역에서는 이러한 경향이 두드러집니다. 덴마크, 일본, 한국 등 각국의 등록 데이터에도 유사한 동향이 기록되어 있으며, 고위험군 선별검사가 인구 수준에서 수요로 변화하고 있습니다. 고령 산모는 더 이른 시점부터 더 빈번하게 산전 관리를 받는 경향이 있어, 검사 기관은 더 빨리 검체를 채취할 수 있게 되었고, 총 검사 건수가 증가하고 있습니다. 이러한 인구 통계학적 동향은 검사 대상 산모층을 확대하는 동시에, 정확하고 위험이 낮은 진단에 대한 임상적 시급성을 높임으로써 비침습적 산전 검사 시장의 장기적인 성장을 뒷받침하고 있습니다.
침습적 염색체 분석에서 cfDNA 선별 검사로의 전환
전문 학회는 현재 cfDNA를 1차 선별 검사로 권장하고 있으며, 기존의 위험도 계층화에 따른 장벽이 해소되었습니다. ACOG의 2024년판 지침에서는 모든 임신에 대해 cfDNA를 권장하고 있는 반면, ACMG의 2025년판 성명에서는 21번 삼염색체증에 대한 검출률이 생화학적 방법으로는 85%인 반면, cfDNA를 사용하면 99% 이상이라는 점을 강조하고 있습니다. 보험사들도 이에 발맞추어, UnitedHealthcare, Centene, Medica는 2024년부터 2025년까지 고위험 근거 제시를 의무화하지 않는 방침으로 전환하며 진료 경로를 혁신했습니다. 양수천자는 여전히 결정적인 검사이지만, 0.1-0.3%의 유산 위험을 수반하기 때문에 현재 많은 환자가 이를 피하고 있으며, 이로 인해 cfDNA 검사 건수가 더욱 증가하고 있습니다. 검사 기관들이 혈청 스크리닝 플랫폼을 폐지함에 따라, 시퀀싱 역량은 검사 항목 확충으로 재분배되고 있으며, 침습적 진단법에서 비침습적 진단법으로의 전환이 가속화되어 비침습적 산전 검사 시장을 견인하고 있습니다.
2차 소견 및 성별 선택을 둘러싼 윤리적 논쟁의 지속
cfDNA에서 나타나는 악성 종양의 징후 등 산모와 관련된 우발적 소견은 정보 공개와 관련된 딜레마를 야기하며, 추가적인 상담 시간과 동의서 작성이 필요하게 됩니다. 인도에서는 감사 결과, PCPNDT법을 위반하여 태아의 성별을 보고했던 클리닉이 적발되어 면허 정지 처분을 받았습니다. 중국에서도 마찬가지로, 의료 목적 이외의 성별 보고가 금지되어 있습니다. 유럽인류유전학회는 현재 2차 소견에 대해 검사 전 명확한 동의를 요구하고 있습니다. 관리상의 부담이 증가함에 따라 검사 제공업체가 주저하거나 검사가 지연되어, 비침습적 산전 검사 시장의 성장이 둔화될 가능성이 있습니다.
부문 분석
기술별 비침습적 산전 검사 시장 규모는 2025년에 39억 달러에 달할 것으로 예상되며, 그중 차세대 염기서열 분석(NGS)이 70.55%를 차지합니다. 한편, RCA 플랫폼은 자본 비용을 대폭 절감하는 간단한 탁상형 하드웨어를 통해 연평균 성장률(CAGR) 18.25%로 급속히 확대되고 있습니다. Clinical Chemistry 저널에 따르면, 21번 삼염색체증 검출에서 RCA와 NGS 간의 일치율은 98.7%로 보고되었으며, 라이브러리 준비 시간은 90분으로 단축되었습니다. NGS는 FDA의 그랜드파더링 및 CE-IVD 검증 경로 덕분에 여전히 확고한 입지를 유지하고 있지만, 소규모 병원에서는 일일 처리 용량 요구 사항을 충족하는 RCA 키트가 선호되고 있습니다.
각 NGS 업체들은 계속해서 처리 능력 향상에 주력하고 있습니다. 일루미나(Illumina)의 NextSeq 2000 멀티플로우셀 아키텍처 덕분에 검사실은 소량의 검사를 유연하게 일괄 처리할 수 있게 되었으며, 한편 써모 피셔(Thermo Fisher)의 Genexus는 검체에서 보고서에 이르기까지의 전 과정을 자동화하고 있습니다. 그럼에도 불구하고, 등온 PCR 공급업체들은 전력 안정성이나 공조·환기(HVAC) 제약으로 인해 기존 시퀀서 사용이 제한되는 라틴아메리카 및 동남아시아의 분산형 네트워크에서 수요를 모으고 있습니다. SNP 조사 기법을 둘러싼 일루미나와 나테라 간의 특허 분쟁이 불확실성을 야기하고 있기 때문에 일부 공급업체는 오픈소스 RCA 대체 기술을 시험적으로 도입하고 있습니다. 전반적으로 기술의 다양화는 공급업체 간의 경쟁을 확대하고, 비침습적 산전 검사 시장의 지속적인 성장을 뒷받침하고 있습니다.
2025년에는 비침습적 산전 검사 시장 점유율의 85.53%를 이수성 패널이 차지했습니다. 한편, 임상의들이 일반적인 삼염색체증 이외의 복제 수 변이(CNV)에 대한 정보를 요구함에 따라, 전체 유전체 cfDNA 스크리닝은 연평균 성장률(CAGR) 19.75%로 성장하고 있습니다. Lancet 지가 9만 건의 임신을 대상으로 실시한 연구에 따르면, 표준 패널 검사에서는 놓쳤던 사례의 1.7%에서 임상적으로 유의미한 CNV가 확인되었습니다. 보험사의 소극적인 태도에도 불구하고, 자비 진료 환자들은 더 광범위한 검사 범위를 선택하고 있으며, 특히 중국에서는 국내산 검사 키트가 450달러 미만의 가격대로 전장 유전체 분석을 포함하고 있는 것이 그 요인으로 작용하고 있습니다.
미세 결실 스크리닝은 미국에서 보험 급여의 장벽에 직면하고 있지만, 독일과 이스라엘에서는 고위험군을 대상으로 보급이 확대되고 있습니다. Rh-D 유전자형 판정은 여전히 틈새 시장이지만, Rhesus 음성 집단에서는 수익이 안정적입니다. 단일 유전자 질환을 대상으로 한 cfDNA 패널이 등장하고 있습니다. 2026년에 Natera가 출시할 예정인 21개 유전자 패널 ‘Fetal Focus’는 추가 채혈이 필요 없는 단일 유전자 검출로의 전환을 보여줍니다. 검증 데이터 세트가 확대됨에 따라, 더 광범위한 패널이 보험사의 인식을 변화시키고 비침습적 산전 검사 시장 내 수익 다각화를 가속화할 가능성이 있습니다.
비침습적 산전 검사 시장 규모 중 임신 13-24주 검사가 50.15%를 차지하고 있습니다. 태아 분획의 추정 정확도를 높이는 알고리즘 덕분에 빠르면 임신 10주부터 신뢰할 수 있는 판정이 가능해졌으며, 임신 10-12주 코호트는 연평균 성장률(CAGR) 14.82%로 확대되고 있습니다. Obstetrics & Gynecology 저널의 데이터에 따르면, 임신 13주 이전에 검사를 받은 환자는 법적으로 허용된 낙태 기한 내에 이상 결과에 근거하여 조치를 취할 가능성이 40% 더 높습니다.
조기 채혈은 원격 의료를 통한 산전 검사 프로그램에 매력적인 요소이며, 1차 진료 클리닉에서 당일 채혈을 가능하게 합니다. 그러나 일본 및 유럽 일부 지역의 초음파를 통한 임신 주수 판정에 대한 엄격한 요건으로 인해 임신 초기 검사 도입이 지연되고 있습니다. 검사 기관은 예측 모델을 활용해 태아 분획률이 낮을 것으로 예상되는 사례를 선별하고, 필요 시 추후 채혈 일정을 잡음으로써 재채혈의 위험을 줄이고 있습니다. 임신 초기 단계에서의 도입 확대는 회전율을 가속화하여 비침습적 산전 검사 시장 전체의 잠재 시장 규모(TAV)를 끌어올릴 것입니다.
지역별 분석
2025년, 북미는 비침습적 산전 검사 시장에서 45.23%의 점유율로 시장을 주도했습니다. 이는 지침에 기반한 보편적 선별 검사와 위험 요건을 철폐한 보험사의 지원에 힘입은 결과입니다. 협상을 통해 결정된 검사 가격은 평균 800-1,200달러로 여전히 높은 수준을 유지하며, 미국 검사 기관들에게 건전한 이익률을 보장하고 있습니다. 캐나다의 보조금 제도는 주마다 다릅니다. 온타리오주에서는 40세 이상의 여성이 대상인 반면, 브리티시컬럼비아주에서는 본인 부담에 의존하고 있어 전국적인 보급률은 35%에 그치고 있습니다. 멕시코의 사립 병원에서는 600-800달러의 검사가 제공되고 있지만, 공공 기관에서는 여전히 생화학적 선별 검사가 주류를 이루고 있습니다.
아시아태평양은 연평균 성장률(CAGR) 16.42%를 기록하며 가장 빠르게 성장하고 있는 지역입니다. 중국 국가약품감독관리국(NMPA)이 BGI 및 Berry Genomics의 플랫폼을 승인함에 따라, 국내 검사 건수는 전년 대비 40% 증가했습니다. 국내 시퀀싱 비용 효율화로 인해 150-300달러의 가격 책정이 가능해지면서, 주요 도시 이외 지역으로의 보급이 확대되고 있습니다. 일본에서는 2025년에 인증 시설 네트워크가 142곳으로 확대되었으나, 신중한 상담 절차로 인해 본격적인 보급은 더딘 양상을 보이고 있습니다. 인도에서는 도시 지역의 중산층이 검사 건수를 주도하고 있으며, 검사당 18,000루피(215달러)이지만, 농촌 지역의 콜드체인 인프라 미비로 인해 전국적인 보급이 제한되고 있습니다.
유럽에서는 IVDR(체외진단용 의료기기 규정) 준수 비용의 영향을 받아 한 자릿수 중반대의 성장률을 보이고 있습니다. 독일에서는 고위험 사례만 공적 자금 지원 대상이지만, 특정 환자의 경우 미세 결실 검사도 공적 보험 적용 대상에 포함됩니다. 영국의 NHS(국민보건서비스)는 임신 초기 선별 검사에서 고위험군으로 판정된 여성에게만 NIPT를 제한하고 있지만, 이러한 대상 제한 정책으로 인해 양수천자 시행 건수는 여전히 60% 감소했습니다. 중동에서의 보급은 UAE가 주도하고 있으며, 해당국에서는 외국인 거주자들이 고품질의 산전 관리를 요구하고 있습니다. 두바이의 검사 기관에서는 연간 25%의 성장률을 보고하고 있습니다. 남미에서는 브라질을 제외한 다른 국가들은 아직 도입 초기 단계이지만, 브라질에서는 Dasa가 2024년에 500달러짜리 NIPT 서비스를 시작했습니다.
기타 혜택:
- 엑셀 형식 시장 예측(ME) 시트
- 3개월간의 애널리스트 지원
자주 묻는 질문
목차
제1장 서론
제2장 조사 방법
제3장 주요 요약
제4장 시장 구도
제5장 시장 규모와 성장 예측
제6장 경쟁 구도
제7장 시장 기회와 향후 전망
JHS 26.09.09According to Mordor Intelligence, the non-invasive prenatal testing market size is projected to expand from USD 3.9 billion in 2025 and USD 4.43 billion in 2026 to USD 8.36 billion by 2031, registering a 13.53% CAGR over 2026-2031.
This report is Segmented by Technology (Next-Generation Sequencing, and More), Test Type (Aneuploidy Screening, and More), Gestation Window (10-12 Weeks, and More), Sample Type (Maternal Plasma CfDNA, and More), Component (Instruments, and More), End User (Hospitals, and More), Distribution Channel, Application, and Geography. The Market Forecasts are Provided in Terms of Value (USD).
Global Non-Invasive Prenatal Testing Market Trends and Insights
Rising Global Maternal Age Elevating Aneuploidy Risk
Women are delaying childbirth for economic and career reasons, pushing the median maternal age higher in every OECD country. In the United States, the mean age at first birth reached 27.8 years in 2024. Age-linked trisomy incidence drives obstetricians to recommend cfDNA screening universally, especially where public programs subsidize testing for women >= 35 years. National registries in Denmark, Japan, and South Korea record parallel shifts, converting high-risk screening into population-level demand. As older mothers often pursue prenatal care earlier and more frequently, laboratories can capture samples sooner, lifting overall test volumes. This demographic trend feeds long-term growth for the non-invasive prenatal testing market by expanding both the eligible base and the clinical urgency for accurate, low-risk diagnostics.
Shift from Invasive Karyotyping to cfDNA Screening
Professional societies now endorse cfDNA as first-line screening, eliminating legacy risk-stratification hurdles. ACOG's 2024 bulletin recommends cfDNA for all pregnancies, while ACMG's 2025 statement highlights > 99% detection for trisomy 21 versus 85% for biochemical methods. Payers have followed suit; UnitedHealthcare, Centene, and Medica stopped requiring high-risk justification in 2024-2025, transforming care pathways. Amniocentesis, though still definitive, carries a 0.1-0.3% loss risk that many patients now avoid, further propelling cfDNA volumes. As laboratories retire serum screening platforms, sequencing capacity is redeployed to support expanded panels, reinforcing the migration away from invasive diagnostics and boosting the non-invasive prenatal testing market.
Persisting Ethical Debate on Secondary Findings & Sex Selection
Incidental maternal findings-such as malignancy signals in cfDNA-raise disclosure dilemmas that require extra counseling time and consent forms. In India, audits uncovered clinics reporting fetal sex in violation of the PCPNDT Act, prompting license suspensions. China similarly bans non-medical sex reporting. The European Society of Human Genetics now urges explicit pre-test consent for secondary findings. Added administrative overhead can deter providers and delay testing, moderating growth in the non-invasive prenatal testing market.
Other drivers and restraints analyzed in the detailed report include:
- Sequencing Cost Curve Less Than USD 200/Sample Enabling Mass Adoption
- Payer Coverage Expansion to Average-Risk Pregnancies
- Bioinformatics Talent Shortage in Emerging Markets
For complete list of drivers and restraints, kindly check the Table Of Contents.
Segment Analysis
The non-invasive prenatal testing market size for technology reached USD 3.9 billion in 2025, with next-generation sequencing accounting for 70.55%. RCA platforms, however, are accelerating at an 18.25% CAGR on simpler, benchtop hardware that slashes capital costs. Clinical Chemistry reported 98.7% concordance between RCA and NGS for trisomy 21 detection, cutting library prep time to 90 minutes. NGS remains entrenched thanks to FDA grandfathering and CE-IVD validation pathways, but small hospitals favor RCA kits that match daily throughput needs.
NGS players continue to enhance throughput; Illumina's NextSeq 2000 multiple-flow-cell architecture allows labs to batch low-volume runs flexibly, while Thermo Fisher's Genexus integrates sample-to-report automation. Even so, isothermal vendors appeal to decentralized networks in Latin America and Southeast Asia where power stability and HVAC constraints limit traditional sequencers. Patent disputes between Illumina and Natera over SNP methodologies inject uncertainty, prompting some providers to trial open-filed RCA alternatives. Overall, technology diversification broadens supplier competition and underpins sustained growth for the non-invasive prenatal testing market.
In 2025, aneuploidy panels held 85.53% of the non-invasive prenatal testing market share. Whole-genome cfDNA screening, meanwhile, is growing at 19.75% CAGR as clinicians seek copy-number variant (CNV) insights beyond common trisomies. The Lancet study of 90,000 pregnancies identified clinically significant CNVs in 1.7% of cases missed by standard panels. Despite payer hesitancy, private patients opt for broader coverage, especially in China where domestic kits bundle genome-wide analysis at sub-USD 450 price points.
Microdeletion screening faces reimbursement roadblocks in the United States but gains traction in Germany and Israel for high-risk cohorts. Rh-D genotyping remains a niche, stabilizing revenues in Rhesus-negative populations. Monogenic disorder cfDNA panels are emerging; Natera's 21-gene Fetal Focus launch in 2026 illustrates a pivot toward single-gene detection without extra blood draws. As validation datasets expand, broader panels could shift payer perspectives, accelerating revenue diversification inside the non-invasive prenatal testing market.
The non-invasive prenatal testing market size tied to the 13-24-week capturing 50.15%. Algorithms that refine fetal-fraction estimates now support reliable calls as early as 10 weeks, propelling the 10-12-week cohort at a 14.82% CAGR. Obstetrics & Gynecology data show patients tested before 13 weeks are 40% likelier to act on abnormal results within legal termination timelines.
Earlier draws appeal to telehealth prenatal programs, permitting same-day phlebotomy at primary-care clinics. However, strict ultrasound dating requirements in Japan and parts of Europe slow first-trimester uptake. Laboratories mitigate redraw risk through predictive models that flag low expected fetal fraction, scheduling later collections when necessary. Wider first-trimester adoption accelerates turnover and elevates total addressable volume across the non-invasive prenatal testing market.
Complete Report Scope:
- By Technology
- Next-Generation Sequencing (NGS)
- Rolling-Circle Amplification
- Microarray
- Real-Time PCR
- Other Technologies
- By Test Type
- Aneuploidy Screening
- Microdeletion / Microduplication Screening
- Whole-Genome cfDNA Screening
- Rh-D Genotyping
- Monogenic Disease Testing
- By Gestation Window
- 10 - 12 Weeks
- 13 - 24 Weeks
- > 24 Weeks
- By Sample Type
- Maternal Plasma cfDNA
- Circulating Trophoblastic Cells
- By Component
- Instruments
- Kits & Reagents
- Services
- By End User
- Hospitals & Birthing Centers
- Diagnostic Laboratories
- IVF & Fertility Clinics
- Research Institutes
- By Distribution Channel
- Physician-Referral
- Direct-to-Consumer (DTC)
- By Application
- Down Syndrome (Trisomy 21)
- Edwards Syndrome (Trisomy 18)
- Patau Syndrome (Trisomy 13)
- Turner Syndrome
- Other Chromosomal Abnormalities
- By Geography
- North America
- United States
- Canada
- Mexico
- Europe
- Germany
- United Kingdom
- France
- Italy
- Spain
- Rest of Europe
- Asia-Pacific
- China
- India
- Japan
- Australia
- South Korea
- Rest of Asia-Pacific
- Middle East and Africa
- GCC
- South Africa
- Rest of Middle East and Africa
- South America
- Brazil
- Argentina
- Rest of South America
- North America
Geography Analysis
North America led the non-invasive prenatal testing market in 2025 with a 45.23% share, supported by guideline-driven universal screening and payers that removed risk prerequisites. Average negotiated test prices remain high at USD 800-1,200, sustaining healthy margins for U.S. labs. Canada's funding varies provincially; Ontario covers women >= 40 years, while British Columbia relies on private pay, capping national penetration at 35%. Mexico's private hospitals offer USD 600-800 tests, but public institutions still default to biochemical screening.
Asia-Pacific is the fastest-growing region at 16.42% CAGR. China's NMPA approvals for BGI and Berry Genomics platforms lifted national test volumes 40% year-over-year. Domestic sequencing economics enable USD 150-300 pricing, expanding access beyond top-tier cities. Japan's certified facility network increased to 142 in 2025, though cautious counseling slows mass adoption. India's urban middle class drives volumes at INR 18,000 (USD 215) per test, yet rural cold-chain gaps limit nationwide reach.
Europe shows mid-single-digit growth influenced by IVDR compliance costs. Germany funds only high-risk cases but covers microdeletions for select patients. The U.K.'s NHS restricts NIPT to women flagged high-risk by first-trimester screens, a targeted policy that still cut amniocentesis 60%. Middle East adoption is led by the UAE, where expatriate populations demand premium prenatal care; Dubai labs report 25% annual growth. Latin America is nascent beyond Brazil, where Dasa launched USD 500 NIPT in 2024.
- Agilent Technologies
- Berry Genomics
- BGI Genomics Co. Ltd
- Centogene
- Eurofins
- F. Hoffmann-La Roche Ltd (Ariosa)
- Fulgent Genetics Inc.
- Genetron Health
- Illumina
- Invitae
- Laboratory Corp of America Holdings (Labcorp)
- MedGenome Labs
- Myriad Women's Health Inc.
- Natera
- QIAGEN
- Ravgen Inc.
- Revvity, Inc.
- Thermo Fisher Scientific
Additional Benefits:
- The market estimate (ME) sheet in Excel format
- 3 months of analyst support
TABLE OF CONTENTS
1 Introduction
- 1.1 Study Assumptions & Market Definition
- 1.2 Scope of the Study
2 Research Methodology
3 Executive Summary
4 Market Landscape
- 4.1 Market Overview
- 4.2 Market Drivers
- 4.2.1 Rising global maternal age elevating aneuploidy risk
- 4.2.2 Shift from invasive karyotyping to cfDNA screening
- 4.2.3 Sequencing cost curve Less Than USD 200/sample enabling mass adoption
- 4.2.4 Payer coverage expansion to average-risk pregnancies
- 4.2.5 AI-assisted fetal fraction calling improving first-trimester accuracy
- 4.2.6 Bundled reproductive-genetic panels (carrier + NIPT) gaining traction
- 4.3 Market Restraints
- 4.3.1 Persisting ethical debate on secondary findings & sex selection
- 4.3.2 Bioinformatics talent shortage in emerging markets
- 4.3.3 Discordant results in multifetal / IVF pregnancies dampen clinician confidence
- 4.3.4 Reimbursement push-back on microdeletion add-ons
- 4.4 Supply-Chain Analysis
- 4.5 Regulatory Landscape
- 4.6 Technological Outlook
- 4.7 Porter's Five Forces
- 4.7.1 Threat of New Entrants
- 4.7.2 Bargaining Power of Buyers
- 4.7.3 Bargaining Power of Suppliers
- 4.7.4 Threat of Substitutes
- 4.7.5 Competitive Rivalry
5 Market Size & Growth Forecasts (Value, USD)
- 5.1 By Technology
- 5.1.1 Next-Generation Sequencing (NGS)
- 5.1.2 Rolling-Circle Amplification
- 5.1.3 Microarray
- 5.1.4 Real-Time PCR
- 5.1.5 Other Technologies
- 5.2 By Test Type
- 5.2.1 Aneuploidy Screening
- 5.2.2 Microdeletion / Microduplication Screening
- 5.2.3 Whole-Genome cfDNA Screening
- 5.2.4 Rh-D Genotyping
- 5.2.5 Monogenic Disease Testing
- 5.3 By Gestation Window
- 5.3.1 10 - 12 Weeks
- 5.3.2 13 - 24 Weeks
- 5.3.3 > 24 Weeks
- 5.4 By Sample Type
- 5.4.1 Maternal Plasma cfDNA
- 5.4.2 Circulating Trophoblastic Cells
- 5.5 By Component
- 5.5.1 Instruments
- 5.5.2 Kits & Reagents
- 5.5.3 Services
- 5.6 By End User
- 5.6.1 Hospitals & Birthing Centers
- 5.6.2 Diagnostic Laboratories
- 5.6.3 IVF & Fertility Clinics
- 5.6.4 Research Institutes
- 5.7 By Distribution Channel
- 5.7.1 Physician-Referral
- 5.7.2 Direct-to-Consumer (DTC)
- 5.8 By Application
- 5.8.1 Down Syndrome (Trisomy 21)
- 5.8.2 Edwards Syndrome (Trisomy 18)
- 5.8.3 Patau Syndrome (Trisomy 13)
- 5.8.4 Turner Syndrome
- 5.8.5 Other Chromosomal Abnormalities
- 5.9 By Geography
- 5.9.1 North America
- 5.9.1.1 United States
- 5.9.1.2 Canada
- 5.9.1.3 Mexico
- 5.9.2 Europe
- 5.9.2.1 Germany
- 5.9.2.2 United Kingdom
- 5.9.2.3 France
- 5.9.2.4 Italy
- 5.9.2.5 Spain
- 5.9.2.6 Rest of Europe
- 5.9.3 Asia-Pacific
- 5.9.3.1 China
- 5.9.3.2 India
- 5.9.3.3 Japan
- 5.9.3.4 Australia
- 5.9.3.5 South Korea
- 5.9.3.6 Rest of Asia-Pacific
- 5.9.4 Middle East and Africa
- 5.9.4.1 GCC
- 5.9.4.2 South Africa
- 5.9.4.3 Rest of Middle East and Africa
- 5.9.5 South America
- 5.9.5.1 Brazil
- 5.9.5.2 Argentina
- 5.9.5.3 Rest of South America
- 5.9.1 North America
6 Competitive Landscape
- 6.1 Market Concentration
- 6.2 Market Share Analysis
- 6.3 Company Profiles (includes Global-level Overview, Market-level Overview, Core Segments, Financials as available, Strategic Information, Market Rank/Share for key companies, Products & Services, and Recent Developments)
- 6.3.1 Agilent Technologies Inc.
- 6.3.2 Berry Genomics
- 6.3.3 BGI Genomics Co. Ltd
- 6.3.4 Centogene N.V.
- 6.3.5 Eurofins Scientific SE
- 6.3.6 F. Hoffmann-La Roche Ltd (Ariosa)
- 6.3.7 Fulgent Genetics Inc.
- 6.3.8 Genetron Health
- 6.3.9 Illumina Inc.
- 6.3.10 Invitae Corporation
- 6.3.11 Laboratory Corp of America Holdings (Labcorp)
- 6.3.12 MedGenome Labs Ltd
- 6.3.13 Myriad Women's Health Inc.
- 6.3.14 Natera Inc.
- 6.3.15 Qiagen N.V.
- 6.3.16 Ravgen Inc.
- 6.3.17 Revvity, Inc.
- 6.3.18 Thermo Fisher Scientific Inc.
7 Market Opportunities & Future Outlook
- 7.1 White-Space & Unmet-Need Assessment














