

|
시장보고서
상품코드
2123368
미국의 독립 응급실 시장 : 점유율 분석, 업계 동향과 통계, 성장 예측(2026-2031년)United States Freestanding Emergency Department - Market Share Analysis, Industry Trends & Statistics, Growth Forecasts (2026 - 2031) |
||||||
 Mordor Intelligence
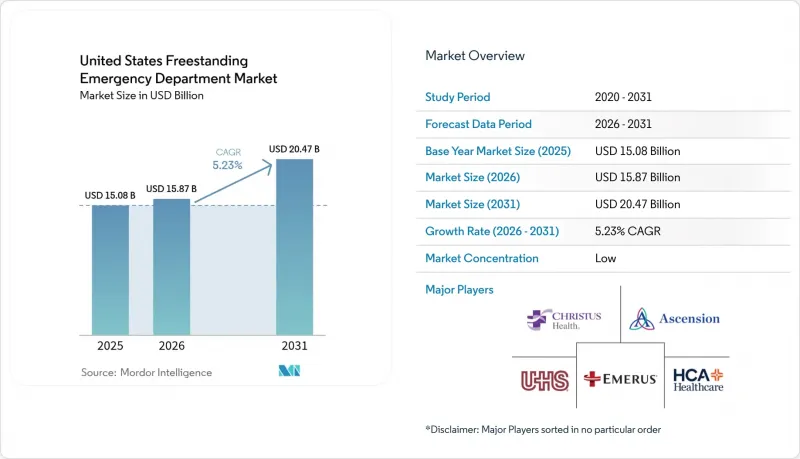
에 의하면, 미국 독립 응급실 시장 규모는 2025년에 150억 8,000만 달러로 평가되었고 2026년 158억 7,000만 달러에서 2031년까지 204억 7,000만 달러에 이를 것으로 예측되며, 예측 기간(2026-2031년) CAGR은 5.23%를 나타낼 전망입니다.
본 보고서는 소유 형태(병원 외 응급실(병원 부속), 독립 응급실), 서비스(응급 의료 및 기타 서비스, 영상 진단 서비스, 검사 서비스), 시설 규모(초소규모, 소규모, 중규모, 대규모) 및 지역(북동부, 중서부, 남부, 서부)별로 분류되어 있습니다. 시장 전망은 금액(달러) 기준으로 제시되어 있습니다.
미국 독립 응급실 시장 동향 및 인사이트
소비자 주도형 의료보험 플랜 및 연방 정부의 보조금 프로그램
연방 보조 프로그램은 대출 상환을 의료 서비스가 부족한 지역으로의 배치를 연계함으로써 자본 측면의 장벽을 낮추고, 인력 부족 해소를 도모하고 있습니다. 2025 회계연도 예산에서는 지역 의료 센터에 대한 자금 지원이 두 배로 늘어나며, 독립 응급실 부문은 3,700만 명의 미국인의 응급 수요를 흡수할 수 있는 의뢰 거점으로서의 입지가 강화되고 있습니다. 2026년에는 연방 정부의 지원이 매우 중요한 역할을 하고 있으며, 그 대표적인 예로 농촌 의료 혁신 프로그램(Rural Health Transformation Program)에 따라 뉴햄프셔주에 2억 400만 달러의 보조금이 배정된 것을 들 수 있습니다. 이 자금은 의료 서비스가 부족한 카운티의 응급·긴급 의료 접근성 향상을 목적으로 2026년부터 2030년까지 시행되는 총액 500억 달러 규모의 광범위한 국가 이니셔티브의 일환입니다. 또한, 원격의료 인프라 구축 및 고급 실무 의료 종사자 연수에도 자금이 투입되어, 현장에 응급의사가 제한적인 지역에서도 연중무휴 24시간 대응이 보장되고 있습니다. 이용 동향에는 소득에 따른 격차가 나타납니다. 고소득층은 시설 이용료가 비싸더라도 시간 절약을 우선시하는 반면, 저소득층은 증상이 악화될 때까지 진료를 미루는 경향이 있습니다. 독립 사업자들은 이러한 이용 패턴에 맞춘 서비스를 제공하기 위해 전략적으로 교외 지역으로 사업을 확장하고 있습니다.
편리성이 높은 의료 서비스에 대한 수요 증가
환자 설문조사에 따르면, 내원부터 의료진과의 면담까지 걸리는 시간이 15분 미만인 것이 시설 선택에 큰 영향을 미치고 있습니다. 독립 응급진료소는 이 기준을 항상 충족하는 반면, 병원 응급실에서는 평균 45분 이상 소요됩니다. 의료 시스템에 의한 응급 치료 체인 인수는 편의성을 중시한 전략적 제휴를 보여줍니다. HCA 헬스케어는 2025년에 텍사스주 내 41개 센터를 인수하여 인근 독립 응급 진료소로 환자를 유도하는 네트워크를 구축했습니다. 출퇴근 경로상에 위치한 시설은 퇴근길 환자를 유치하고, 혼잡한 병원 캠퍼스에서 생명에 지장이 없는 증례를 우회시키고 있습니다. 응급 치료와 응급 의료 허가를 결합한 하이브리드 시설에서는 시설 내 의사가 내원자의 약 70%를 중증도가 낮은 진료 코스로 유도할 수 있어, 응급 의료 기능을 유지하면서 환자의 경제적 부담을 경감시키고 있습니다.
1회 진료당 총 비용의 높음: 응급 진료 대안과의 비교
독립 응급실에서는 중증도에 관계없이 1회 진료당 보통 1,500-3,000달러의 시설 이용료를 청구하는 반면, 많은 저복잡도 질환에 대한 긴급 진료의 경우 100-200달러 정도에 불과하기 때문에 소비자의 비용에 대한 우려와 평판 리스크가 높아지고 있습니다. 민간 보험사는 사전 승인, 네트워크 설계 및 단계적 비용 분담을 통해 피할 수 있는 진료를 저비용 시설로 유도하는 조치를 취하고 있으며, 그 결과 고액의 본인 부담 비용을 지불할 의사가 있는 민간 보험 가입 환자층이 좁아지고 있습니다. 고액 공제형 보험 플랜의 설계는 이러한 마찰을 더욱 증폭시키고 있습니다. 가입자는 공제액에 도달할 때까지 시설 이용료 전액을 지불해야 하기 때문에 나중에 진료가 네트워크 외로 처리되었습니다는 사실을 알게 된 환자들로부터 부정적인 평가가 쏟아지는 원인이 되고 있습니다. 한편, 응급 진료망은 진료 시간 연장, 시설 내 진단 기능 확충, 명확한 요금 공표 등의 조치를 취하며, 경미한 질병이나 부상을 입은 환자 유치를 놓고 편의성을 무기로 직접적인 경쟁을 펼치고 있습니다.
부문 분석
2025년, 캠퍼스 외부 응급 부문은 통합된 전자 의료 기록, 유리한 메디케어 파트 B 청구 조건, 그리고 병원에서 유입되는 환자 흐름을 활용하여 미국 독립 응급실 시장에서 58.02%의 점유율을 차지했습니다. 독립 센터는 전체 규모는 작지만, 병원 서비스가 미치지 못하는 카운티의 규제 허점을 기업이 그룹이 활용함으로써 2031년까지 연평균 성장률(CAGR) 5.87%를 나타낼 것으로 예측됩니다.
병원 그룹은 캠퍼스 외 응급실을 경쟁사를 견제하기 위한 전략적 발판으로 계속해서 포지셔닝하고 있습니다. HCA Florida사가 파스코 카운티, 헤르난도 카운티, 시트러스 카운티에 3곳의 신규 시설을 개설하는 7,000만 달러 규모의 계획은 급성장하는 주택 개발 지역으로부터 10마일 반경 내에 브랜드화된 응급 의료 접근성을 배치하는 자산을 최소화한 확장 전략의 한 예입니다. 이에 반해, 독립 운영업체들은 소아 외상 및 고령자 전용 환경에 특화하여, 트라이아지 대기 시간이 짧다는 점이나 컨시어지 스타일의 시설 등을 통해 차별화를 꾀하고 있습니다.
기타 혜택:
- 엑셀 형식 시장 예측(ME) 시트
- 3개월간의 애널리스트 지원
자주 묻는 질문
목차
제1장 서론
제2장 조사 방법
제3장 주요 요약
제4장 시장 구도
제5장 시장 규모와 성장 예측
제6장 경쟁 구도
제7장 시장 기회와 향후 전망
JHS 26.09.11According to Mordor Intelligence, the United States freestanding emergency department market size was valued at USD 15.08 billion in 2025 and is estimated to grow from USD 15.87 billion in 2026 to reach USD 20.47 billion by 2031, at a CAGR of 5.23% during the forecast period (2026-2031).
This report is Segmented by Ownership Type (Off-Campus Emergency Departments, Independent Freestanding Emergency Departments), Service (Emergency Care & Other Services, Imaging Services, Laboratory Services), Facility Size (Micro, Small, Medium, Large), and Geography (Northeast, Midwest, South, West). Market Forecasts are Provided in Terms of Value (USD).
United States Freestanding Emergency Department Market Trends and Insights
Consumer-Driven Health Plans and Federal Grant Programmes
Federal grant programs lower capital barriers and address workforce shortages by tying loan repayments to medically underserved areas. The FY 2025 budget doubles community health center financing, positioning freestanding emergency departments as referral anchors that can absorb emergency demand for 37 million Americans. In 2026, federal support plays a pivotal role, highlighted by a USD 204 million grant allocated to New Hampshire under the Rural Health Transformation Program. This funding is part of a broader USD 50 billion national initiative spanning 2026 to 2030 aimed at enhancing access to emergency and urgent care in underserved counties. Additional funding is directed toward telehealth infrastructure and advanced practice provider training, ensuring 24/7 coverage in areas with limited on-site emergency physicians. Utilization trends indicate a divide by income: higher earners prioritize time savings despite higher facility fees, while lower-income individuals often delay visits until conditions worsen. Independent operators are strategically expanding into suburban areas, offering services that align with these utilization patterns.
Rising Demand for Convenience-Care Access
Patient surveys show that door-to-provider times under 15 minutes strongly influence facility choice; freestanding emergency departments routinely meet this threshold, whereas hospital EDs average 45 minutes or more. Health-system acquisitions of urgent-care chains illustrate strategic alignment around convenience: HCA Healthcare acquired 41 Texas centers in 2025 to create feeder networks for nearby freestanding EDs. Facilities situated along commuter routes capture after-work traffic and divert non-life-threatening cases from congested hospital campuses. Hybrid facilities that combine urgent-care and emergency licensure allow on-site physicians to direct nearly 70% of visits to lower-acuity billing, improving patient affordability while preserving emergency capabilities.
High Total Cost Per Visit Vs Urgent-Care Alternatives
Freestanding emergency departments typically charge facility fees of USD 1,500 to USD 3,000 per visit across acuity levels, compared to USD 100 to USD 200 in urgent care for many low-complexity conditions, raising consumer cost concerns and reputational risk. Commercial payers are responding with prior authorization, network design, and differential cost-sharing to steer avoidable visits to lower-cost sites, thereby narrowing the pool of commercially insured patients willing to absorb higher out-of-pocket costs. High-deductible plan designs amplify this friction because members pay the full facility fee until they reach deductibles, which drives negative reviews when patients later learn their visit was processed as out-of-network. Urgent care chains are countering convenience by expanding late hours, adding on-site diagnostics, and publishing clear prices to compete head-to-head for minor illnesses and injuries.
Other drivers and restraints analyzed in the detailed report include:
- Expansion of Hospital Outpatient Strategies
- Rapid Uptake of AI-Enabled Triage and Ambient Documentation
- CMS Reimbursement and Billing-Policy Volatility
For complete list of drivers and restraints, kindly check the Table Of Contents.
Segment Analysis
Off-campus emergency departments held a 58.02% share of the United States freestanding emergency department market in 2025, leveraging integrated electronic health records, favorable Medicare Part B billing, and hospital referral streams. Independent centers, though smaller in aggregate footprint, are projected to outpace at a 5.87% CAGR through 2031 as entrepreneurial groups exploit regulatory gaps in counties underserved by hospitals.
Hospital systems continue to treat off-campus units as strategic beachheads that deter competitors. HCA Florida's USD 70 million plan to open three new sites across Pasco, Hernando, and Citrus Counties exemplifies an asset-light expansion play that places branded emergency access within 10 miles of growing subdivisions. Independent operators counter by specializing in pediatric trauma or geriatric-friendly environments, differentiating on shorter triage queues and concierge-style amenities.
Complete Report Scope:
- By Ownership Type
- Off-Campus Emergency Departments (Hospital-affiliated)
- Independent Freestanding Emergency Departments
- By Service
- Emergency Care & Other Services
- Imaging Services
- Laboratory Services
- By Facility Size (Bed Count)
- Micro (<10 beds)
- Small (10-19 beds)
- Medium (20-29 beds)
- Large (>30 beds)
- By U.S. Census Region
- Northeast
- Midwest
- South
- West
List of Companies Covered in this Report:
- Adeptus Health LLC
- AdventHealth
- Ardent Health Services
- Ascension Health
- Baylor Scott & White Health
- CHRISTUS Health
- CommonSpirit Health
- Community Health Systems, Inc. (CHS)
- Emerus Hospital Partners, LLC
- Envision Healthcare
- HCA Healthcare, Inc.
- Intuitive Health
- LifePoint Health, Inc.
- Northwell Health Inc.
- SignatureCare Emergency Center
- Sutter Health
- Team Health Holdings, Inc.
- Tenet Healthcare
- Universal Health Services
- US Acute Care Solutions
Additional Benefits:
- The market estimate (ME) sheet in Excel format
- 3 months of analyst support
TABLE OF CONTENTS
1 Introduction
- 1.1 Study Assumptions & Market Definition
- 1.2 Scope of the Study
2 Research Methodology
3 Executive Summary
4 Market Landscape
- 4.1 Market Overview
- 4.2 Market Drivers
- 4.2.1 Consumer-Driven Health Plans & Federal Grant Programmes
- 4.2.2 Rising Demand for Convenience-Care Access
- 4.2.3 Expansion of Hospital Outpatient Strategies
- 4.2.4 Rapid Uptake of AI-Enabled Triage and Ambient Documentation
- 4.2.5 Hybrid ED/Urgent-Care Co-Licensing Models
- 4.2.6 State-Level Regulatory Easing (CON Exemptions)
- 4.3 Market Restraints
- 4.3.1 High Total Cost Per Visit Vs Urgent-Care Alternatives
- 4.3.2 CMS Reimbursement & Billing-Policy Volatility
- 4.3.3 Price-Transparency Pressure on Facility Fees
- 4.3.4 Staffing Shortages & Wage Inflation
- 4.4 Value Chain Analysis
- 4.5 Regulatory Landscape
- 4.6 Technological Outlook
- 4.7 Porter's Five Forces Analysis
- 4.7.1 Threat of New Entrants
- 4.7.2 Bargaining Power of Buyers
- 4.7.3 Bargaining Power of Suppliers
- 4.7.4 Threat of Substitutes
- 4.7.5 Intensity of Competitive Rivalry
5 Market Size & Growth Forecasts (Value, USD)
- 5.1 By Ownership Type
- 5.1.1 Off-Campus Emergency Departments (Hospital-affiliated)
- 5.1.2 Independent Freestanding Emergency Departments
- 5.2 By Service
- 5.2.1 Emergency Care & Other Services
- 5.2.2 Imaging Services
- 5.2.3 Laboratory Services
- 5.3 By Facility Size (Bed Count)
- 5.3.1 Micro (<10 beds)
- 5.3.2 Small (10-19 beds)
- 5.3.3 Medium (20-29 beds)
- 5.3.4 Large (>30 beds)
- 5.4 By U.S. Census Region
- 5.4.1 Northeast
- 5.4.2 Midwest
- 5.4.3 South
- 5.4.4 West
6 Competitive Landscape
- 6.1 Market Concentration
- 6.2 Market Share Analysis
- 6.3 Company Profiles (includes Global level Overview, Market-level Overview, Core Segments, Financials, Strategic Information, Market Rank/Share, Products & Services, Recent Developments)
- 6.3.1 Adeptus Health LLC
- 6.3.2 AdventHealth
- 6.3.3 Ardent Health Services
- 6.3.4 Ascension Health
- 6.3.5 Baylor Scott & White Health
- 6.3.6 CHRISTUS Health
- 6.3.7 CommonSpirit Health
- 6.3.8 Community Health Systems, Inc. (CHS)
- 6.3.9 Emerus Hospital Partners, LLC
- 6.3.10 Envision Healthcare Corporation
- 6.3.11 HCA Healthcare, Inc.
- 6.3.12 Intuitive Health
- 6.3.13 LifePoint Health, Inc.
- 6.3.14 Northwell Health Inc.
- 6.3.15 SignatureCare Emergency Center
- 6.3.16 Sutter Health
- 6.3.17 Team Health Holdings, Inc.
- 6.3.18 Tenet Healthcare Corporation
- 6.3.19 Universal Health Services, Inc.
- 6.3.20 US Acute Care Solutions
7 Market Opportunities & Future Outlook
- 7.1 White-space & Unmet-Need Assessment


