

|
시장보고서
상품코드
2119370
심장대사 질환 치료제 : 시장 점유율 분석, 업계 동향 및 통계, 성장 예측(2026-2031년)Cardiometabolic Drugs - Market Share Analysis, Industry Trends & Statistics, Growth Forecasts (2026 - 2031) |
||||||
 Mordor Intelligence
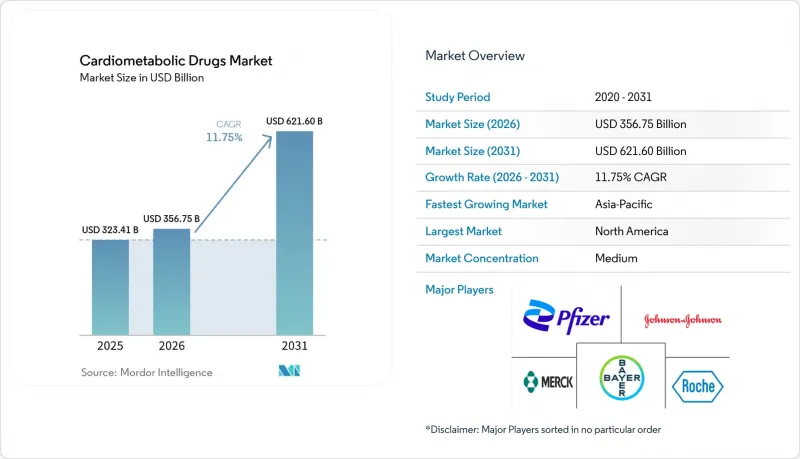
에 의하면, 심장대사 질환 치료제 시장 규모는 2025년에 3,234억 1,000만 달러로 평가되었습니다. 2026년에 3,567억 5,000만 달러에 달하고, 2031년까지 6,216억 달러에 이를 것으로 예측되며, 2026년부터 2031년에 걸쳐 CAGR 11.75%로 성장할 전망입니다.
본 보고서는 치료 분야(당뇨병, 비만·체중 관리, 심혈관 질환(CVD), 심부전·심신증, 대사성 간질환), 약물 분류별(GLP-1 및 인크레틴 계열 약물 등),분자/제품(세마글루티드 등), 투여 경로(경구 투여 등), 제형(정제 및 캡슐 등), 환자 유형(당뇨병, 비만 등), 유통 채널(병원 등), 지역
세계의 심장대사 질환 치료제 시장 동향 및 인사이트
증가하는 심대사성 질환의 부담과 치료 격차
심장대사 질환 치료제 시장은 치료받지 못한 환자 수가 많고, 또한 증가 추세에 있다는 점에 힘입고 있습니다. 국제당뇨병연맹(IDF)의 보고에 따르면, 2024년 성인 당뇨병 환자 수는 5억 8,900만 명이며, 이 중 2억 5,170만 명은 미진단 성인이었습니다. 미진단 사례의 86.9%는 저·중소득 국가에 집중되어 있으며, 이는 조기 치료를 방해하고 향후 합병증의 위험을 높이고 있습니다. 심혈관계 장애 및 사망률은 공복 시 혈장 포도당 수치나 체질량 지수(BMI)와 같은 대사 위험 요인을 점점 더 반영하고 있습니다. 당뇨병은 치료가 지연될 경우 심혈관 질환, 신기능 저하, 대사성 간 질환으로 진행될 가능성이 있습니다. 이러한 관련 질환들은 개별 의약품에 가격 압박이 가해지고 있는 상황에서도 처방 수요를 지속적으로 뒷받침하고 있습니다.
인크레틴, SGLT2 및 위험 감소 요법의 다중 적응증으로의 확대
인크레틴 계열 치료제는 현재 초기 당뇨병 치료의 범위를 넘어, 보다 광범위한 심혈관 및 대사 관리 요구에 부응하고 있습니다. 웨고비(Wegovy)는 2025년 8월, 비간경변성 MASH 및 중등도에서 중증의 간섬유증을 가진 성인 환자에 대한 FDA 승인을 획득했습니다. 이러한 진전을 통해, 그동안 내분비학 및 비만 치료가 중심이었던 치료 경로에 간학이 추가되었습니다. SGLT2 억제제도 2형 당뇨병, 심부전, 만성 신장병 분야에서 계속해서 중요한 역할을 수행하고 있습니다. 임상 및 규제상의 진전을 통해 새로운 분자 군을 도입하지 않고도 적격 환자 수를 확대할 수 있습니다. 위험 감소를 조기에 시작함으로써, 순환기내과 및 신장내과 전문의가 더 이른 단계에서 치료 결정에 관여하게 될 것입니다. 관련 질환에 걸친 통합 치료가 근거와 첨부 문서로 뒷받침됨에 따라, 심장대사 질환 치료제 시장은 혜택을 받게 될 것입니다.
높은 본인 부담금, 보험사의 규제, 그리고 치료 지속의 장벽
가격의 적정성 여부는 고비용의 심대사 치료, 특히 비만 치료에서 여전히 큰 제약 요인으로 작용하고 있습니다. 2025년에는 미국 보험 거래소 플랜의 약제 급여 중 70%가 이용 관리 대상이 되었습니다. 사전 승인이나 단계적 치료(step therapy)는 적격 환자의 치료 시작을 지연시킬 가능성이 있습니다. 당뇨병이나 심혈관 질환의 진단 기록이 없는 비만 환자의 경우, 보험 적용을 받는 것이 더 어려워지는 경우가 많습니다. 또한, 치료의 지속성은 처방 시작 후의 실제 수요에도 영향을 미칩니다. 기업은 조기 중단을 억제하기 위해 환자 지원, 명확한 임상적 사후 관리, 그리고 적절한 가격 책정이 필요합니다. 이러한 접근상의 제약으로 인해 근본적인 임상적 필요성이 높음에도 불구하고 치료 건수가 감소할 가능성이 있습니다.
부문 분석
2025년, 당뇨병은 확고한 처방 기반을 바탕으로 심장대사 질환 치료제 시장의 32.4% 점유율을 차지했습니다. 인슐린, DPP-4 억제제, SGLT2 억제제 및 GLP-1 작용제는 여전히 당뇨병 치료의 핵심을 이루고 있습니다. 비만 및 체중 관리 분야는 2031년까지 연평균 성장률(CAGR) 12.5%를 나타낼 것으로 예측됩니다. 인크레틴 제제의 새로운 적응증 및 치료 경로의 확대로 인해, 비만 치료는 내분비학, 순환기학, 그리고 1차 진료 현장으로 확대되고 있습니다. 인크레틴 요법은 혈당 관리에 그치지 않는 치료 논의의 폭을 넓히고 있습니다. 심혈관 위험 감소 및 간 질환에 대한 적응증은 여러 전문 분야에 걸친 치료를 뒷받침하고 있습니다. 고혈압이나 이상지질혈증은 지속적인 약물 복용이 필요하기 때문에 심혈관 질환은 여전히 중요한 치료 영역으로 남아 있습니다. SGLT2 억제제가 여러 관련 질환에 유효한 만큼, 심부전 및 심신장 질환도 성장하고 있는 치료 영역입니다. 심대사계 의약품 시장은 개별 질환 범주라기보다는 중복되는 환자의 요구를 점점 더 반영하는 추세입니다.
대사성 간 질환은 상업적으로는 소규모 영역이지만, 최근의 승인으로 그 중요성이 높아지고 있습니다. Rezdiffra는 2025년 8월 유럽연합(EU)에서 조건부 승인을 획득했습니다. 영국에서는 2026년 6월, MASH(비간경변성 알코올성 지방간염) 성인 환자에 대한 Rezdiffra의 승인이 내려졌습니다. 또한 Wegovy도 2025년에 비간경변성 MASH에 대해 FDA 승인을 획득했습니다. 이러한 움직임으로 인해 MASH에 대한 승인된 치료법은 두 가지가 되었습니다. 또한, 이로 인해 간 전문의들도 보다 광범위한 심대사 치료 경로에 참여하게 될 것입니다. 비만, 당뇨병, 간 질환 프로그램을 보유한 기업은 자사의 전체 포트폴리오에 공통적으로 적용되는 환자 위험 요인을 활용할 수 있습니다. 이에 따라 예측 기간 동안 치료 영역의 경계는 더욱 모호해질 것입니다.
2025년, 지질강하제는 심장대사 질환 치료제 시장 규모의 24.3%를 차지했습니다. 스타틴은 확립된 치료법이며, 구하기 쉽고 많은 의료 시스템에서 널리 사용되고 있기 때문에 여전히 광범위하게 사용되고 있습니다. PCSK9 억제제 및 siRNA 기반 약물은 확정 진단을 받은 ASCVD 환자나 스타틴 불내성 환자를 돕고 있습니다. GLP-1 및 인크레틴 계열 치료제는 2031년까지 연평균 성장률(CAGR) 12.5%를 나타낼 것으로 예측됩니다. 이러한 치료제의 임상적 적용 범위는 현재 비만, 당뇨병, 심혈관 위험 및 MASH(대사성 신장병)까지 확대되고 있습니다. SGLT2 억제제는 2형 당뇨병, 심부전 및 만성 신장 질환에서 계속해서 중요한 역할을 하고 있습니다. 인슐린 및 기존 항당뇨병제는 비용 중심 시장에서 여전히 중요한 위치를 차지하고 있습니다. 항고혈압제는 브랜드 제품의 가격 결정력이 제한적인 경우에도 계속해서 높은 처방량을 유지하고 있습니다.
항응고제 및 항혈소판제는 지역에 따라 매출 추이가 다릅니다. 유럽에서는 브랜드 제품인 아피사반 및 리발록사반이 제네릭 의약품의 압박에 직면해 있습니다. 미국에서 이러한 약물의 위상은 브랜드 의약품으로서의 치료 용도와 더 광범위한 보험 적용에 의해 계속해서 뒷받침되고 있습니다. 또한, 단일 의약품이 여러 심혈관 및 대사 위험 인자를 동시에 다루는 경우, 약물 군 간에 간접적인 경쟁이 발생할 가능성도 있습니다. 『랜싯』지는 GLP-1 수용체 작용제 및 차세대 인크레틴 요법이 심혈관·대사 질환 관리에서 수행하는 역할이 확대되고 있다고 보도했습니다. 인크레틴 요법의 적응증 확대는 이상지질혈증 치료나 심혈관 치료에 관한 지불 기관의 의사결정을 변화시킬 가능성이 있습니다. 이로 인해 경쟁은 단일 표적 모델에서 보다 광범위한 임상적 가치 모델로 전환될 것입니다. 따라서 심혈관·대사 치료제 업계는 제네릭 의약품의 압박과 약물 분류 간 경쟁을 모두 관리해야 합니다.
세마글루티드는 2025년 매출의 8.7%를 차지하며 개별 분자 중 중요한 위치를 확립했습니다. 그 용도는 주사제 및 경구제, 2형 당뇨병, 비만, 심혈관 위험 감소, 신장 질환, MASH(대사 관련 복부 비만 증후군)에 이릅니다. 틸제파티드는 2031년까지 연평균 성장률(CAGR) 12.1%를 나타낼 것으로 예측됩니다. GIP와 GLP-1의 이중 작용기전을 통해 비만 및 당뇨병 치료 분야에서 독보적인 임상적 위상을 확립하고 있습니다. 엠파글리플로진과 다파글리플로진은 심부전 및 만성 신장 질환 치료에서 여전히 중요한 역할을 하고 있습니다. 아토르바스타틴과 로스바스타틴은 제네릭 의약품의 판매량이 여전히 많은 상황입니다. 아피사반과 리바록사반은 제네릭 의약품의 등장으로 가격 압박에 직면해 있습니다. 따라서 분자 수준에서의 성장은 새로운 치료제에 집중되고 있는 반면, 성숙한 분자들은 폭넓은 접근성을 유지하고 있습니다.
이러한 집중화로 인해 제조 및 제품 공급 확보의 중요성이 커지고 있습니다. 주사용 펩타이드의 제조에는 전문적인 충전·마무리 능력과 기기 조립 능력이 필요합니다. 새로운 적응증의 승인으로 인해 공급 능력 확대를 앞지르는 속도로 수요가 발생할 가능성이 있습니다. 각 기업은 치료법이 상업적 규모를 충분히 달성하기 전에 투자를 진행해야 합니다. 경구용 저분자 치료제는 기존의 제조 인프라를 더 많이 활용할 가능성이 있습니다. 이러한 차이는 특허 만료 후 경쟁 양상에 영향을 미칠 수 있습니다. 제품의 성공 여부는 임상적 근거, 공급의 신뢰성, 투여 형태 및 보험 급여 여부에 좌우될 것입니다. 소수의 플랫폼 분자가 새로운 가치의 대부분을 차지하는 경우, 심장대사 질환 치료제 시장은 취약한 상황에 노출될 수 있습니다.
지역별 분석
2025년, 북미는 심장대사 질환 치료제 시장 점유율의 41.3%를 차지했습니다. 미국에서는 높은 의약품 가격, 광범위한 지침에 기반한 사용, 그리고 근거 기반 치료법의 적극적인 도입이 결합되어 있습니다. GLP-1 및 SGLT2 계열 의약품은 확립된 전문의 네트워크와 적격 환자에 대한 보험사의 급여 대상 지정으로 인해 혜택을 보고 있습니다. 캐나다에서는 주별 처방약 목록 수립 절차 및 의료 기술 평가를 통해 의약품 접근성을 관리하고 있습니다. 멕시코에서는 유통망의 발전에 따라 비급여 비만 치료 채널이 확대되고 있습니다. 미국의 지불 기관에 의한 관리는 고가 의약품에 있어 여전히 제약 요인으로 작용하고 있습니다. ‘인플레이션 억제법’ 또한 메디케어 및 민간 보험 플랜의 벤치마크에서 가격 책정과 관련된 고려 사항을 야기하고 있습니다. 접근 규제가 강화되는 상황 속에서도 북미는 브랜드 의약품 매출에 있어 여전히 중요한 시장으로 남아 있습니다.
유럽은 심장대사 질환 치료제 시장에서 두 번째로 큰 규모를 자랑하는 지역입니다. 독일, 영국, 프랑스, 이탈리아, 스페인이 이 지역 수요 대부분을 차지하고 있습니다. 유럽에서는 질병 부담이 큰 경우, 브랜드 의약품 가격이 북미보다 낮습니다. 보상 결정에는 일반적으로 의료 기술 평가나 치료 성과에 대한 증거가 요구됩니다. 2025년 ‘레즈디프라(Rezdiffra)’의 유럽 승인 및 2026년 영국의 승인으로 인해 MASH(혼합형 당화 증후군)의 치료 선택지가 확대되었습니다. 또한, 제네릭 의약품과의 경쟁으로 인해 항응고제 및 SGLT2 억제제의 매출에 압박이 가해질 것으로 예측됩니다. 이 지역에서는 임상적 근거가 중시되는 반면, 체계화된 가격 책정 및 보험 급여 승인 절차로 인해 매출이 제한되고 있습니다.
아시아태평양은 2031년까지 연평균 성장률(CAGR) 12.2%를 나타낼 것으로 예측되며, 이는 지역별 성장률 중 가장 높은 수치입니다. 중국과 인도는 당뇨병 환자 수가 많으며, 새로운 치료법에 대한 접근 경로도 확대되고 있습니다. 인도의 애보트와 노보노르디스크간의 제휴는 광범위한 유통 시스템의 필요성을 보여줍니다. 일본은 광범위한 보험 적용 범위와 정기적인 가격 조정을 동시에 갖추고 있습니다. 중동 및 아프리카, 남미는 여전히 규모는 작지만 지속적으로 확대되고 있는 지역입니다. 사우디아라비아, 남아프리카공화국, 브라질, 아르헨티나에서는 도시화와 식생활의 변화로 인해 심혈관 및 대사 질환 위험이 높아지고 있습니다. 높은 본인 부담금과 콜드체인 요건으로 인해 주요 대도시권 이외의 지역에서는 주사제 접근성이 제한되고 있습니다. 이러한 지역은 판매량 측면에서 잠재력을 지니고 있으나, 합리적인 가격과 의료 시스템의 수용 능력이 여전히 결정적인 요소로 작용합니다.
기타 혜택 :
- 엑셀 형식 시장 예측(ME) 시트
- 3개월간의 애널리스트 지원
자주 묻는 질문
목차
제1장 서론
제2장 조사 방법
제3장 주요 요약
제4장 시장 구도
제5장 시장 규모 및 성장 예측
제6장 경쟁 구도
제7장 시장 기회 및 향후 전망
KTH 26.09.10According to Mordor Intelligence, the cardiometabolic drugs market size is projected to be USD 323.41 billion in 2025, USD 356.75 billion in 2026, and reach USD 621.60 billion by 2031, growing at a CAGR of 11.75% from 2026 to 2031.
This report is Segmented by Therapeutic Area (Diabetes; Obesity & Weight Management; CVDs; Heart Failure & Cardiorenal; Metabolic Liver Diseases), Drug Class (GLP-1 & Incretin-Based and More), Molecule/Product (Semaglutide and More), Route (Oral and More), Formulation (Tablets & Capsules, and More ), Patient Type (Diabetes, Obesity, and More), Distribution Channel (Hospital and More), and Geography
Global Cardiometabolic Drugs Market Trends and Insights
Rising Cardiometabolic Disease Burden and Treatment Gaps
The cardiometabolic drugs market is supported by a large and growing pool of untreated patients. The International Diabetes Federation reported 589 million adults with diabetes in 2024, including 251.7 million undiagnosed adults. Low- and middle-income countries accounted for 86.9% of undiagnosed cases, which limits early treatment and increases later complications. Cardiovascular disability and mortality increasingly reflect metabolic risks, including high fasting plasma glucose and high body mass index. Diabetes can progress into cardiovascular disease, kidney decline, and metabolic liver disease when treatment is delayed. These linked conditions sustain prescription demand even when pricing pressure affects individual medicines.
Multi-Indication Expansion of Incretin, SGLT2, and Risk-Reduction Therapies
Incretin therapies now reach beyond their original diabetes use and serve wider cardiometabolic care needs. Wegovy received FDA approval for adults with noncirrhotic MASH and moderate-to-advanced liver fibrosis in August 2025. This development brought hepatology into a treatment pathway previously centered on endocrinology and obesity care. SGLT2 inhibitors also remain relevant across type 2 diabetes, heart failure, and chronic kidney disease. Clinical and regulatory developments can expand the number of eligible patients without requiring a new molecular class. Earlier risk reduction may also bring cardiologists and nephrologists into treatment decisions sooner. The cardiometabolic drugs market benefits when evidence and labeling support integrated care across related conditions.
High Out-of-Pocket Costs, Payer Controls, and Persistence Friction
Affordability remains a major limitation for high-cost cardiometabolic treatments, especially for obesity care. Utilization management affected 70% of U.S. exchange-plan drug coverage in 2025. Prior authorization and step therapy can delay treatment starts for eligible patients. Coverage is often more difficult for obesity patients without documented diabetes or cardiovascular disease. Treatment persistence also affects realized demand after a prescription begins. Companies need patient support, clear clinical follow-up, and suitable pricing arrangements to limit early discontinuation. These access constraints can reduce treated volumes despite high underlying clinical need.
Other drivers and restraints analyzed in the detailed report include:
- Oral and Long-Acting Formats Reducing Administration Friction
- Emerging-Market Diagnosis, Coverage, and Reimbursement Expansion
- Generic Erosion, Price Compression, and Product-Security Risk
For complete list of drivers and restraints, kindly check the Table Of Contents.
Segment Analysis
Diabetes held 32.4% of the cardiometabolic drugs market share in 2025, supported by a deep prescription base. Insulin, DPP-4 inhibitors, SGLT2 inhibitors, and GLP-1 agonists remain central to diabetes care. Obesity and weight management is forecast to grow at a 12.5% CAGR through 2031. New incretin labels and broader treatment pathways are bringing obesity care into endocrinology, cardiology, and primary care settings. Incretin therapies have expanded the treatment discussion beyond blood glucose management. Cardiovascular risk reduction and liver disease labels support care across multiple specialties. Cardiovascular diseases remain a large treatment cluster because hypertension and dyslipidemia require sustained medication use. Heart failure and cardiorenal disease are also growing treatment areas because SGLT2 inhibitors serve several related conditions. The cardiometabolic drugs market increasingly reflects overlapping patient needs rather than separate disease categories.
Metabolic liver disease is a smaller commercial area, but recent approvals have increased its relevance. Rezdiffra received conditional authorization in the European Union during August 2025. The UK authorized Rezdiffra for adults with MASH in June 2026. Wegovy also received FDA approval for noncirrhotic MASH during 2025. These events provide 2 approved treatment approaches for MASH. They also bring liver specialists into broader cardiometabolic treatment pathways. Companies with obesity, diabetes, and liver disease programs can use common patient-risk factors across their portfolios. This makes therapeutic-area boundaries less distinct over the forecast period.
Lipid-lowering drugs accounted for 24.3% of the cardiometabolic drugs market size in 2025. Statins retain broad use because they are established, accessible, and used across many health systems. PCSK9 inhibitors and siRNA-based agents support patients with established ASCVD or statin intolerance. GLP-1 and incretin-based therapies are forecast to grow at a 12.5% CAGR through 2031. Their clinical reach now includes obesity, diabetes, cardiovascular risk, and MASH. SGLT2 inhibitors retain a strong role in type 2 diabetes, heart failure, and chronic kidney disease. Insulin and traditional antidiabetic drugs remain important in cost-sensitive markets. Antihypertensives continue to provide high prescription volumes with limited branded pricing power.
Anticoagulants and antiplatelet medicines have different regional revenue paths. Branded apixaban and rivaroxaban face generic pressure in Europe. Their U.S. position remains supported by branded treatment use and broader reimbursement. Drug classes may also compete indirectly when a single medicine addresses several cardiometabolic risk factors. The Lancet described the expanding role of GLP-1 receptor agonists and next-generation incretin therapies in cardiometabolic care. Broader incretin labels could change payer decisions around separate lipid and cardiovascular therapies. This shifts competition from a single-target model toward a wider clinical-value model. The cardiometabolic drugs industry must therefore manage both generic pressure and cross-class competition.
Semaglutide held 8.7% of revenue in 2025, giving it a substantial position among individual molecules. Its use spans injectable and oral formats, type 2 diabetes, obesity, cardiovascular risk reduction, kidney disease, and MASH. Tirzepatide is forecast to grow at a 12.1% CAGR through 2031. Its dual GIP and GLP-1 mechanism supports a distinct clinical position in obesity and diabetes treatment. Empagliflozin and dapagliflozin remain important for heart failure and chronic kidney disease care. Atorvastatin and rosuvastatin continue to contribute high generic volumes. Apixaban and rivaroxaban face price pressure as generic alternatives become available. Molecule-level growth is therefore concentrated in newer therapies while mature molecules sustain broad access.
This concentration increases the importance of manufacturing and product availability. Injectable peptide production requires specialized fill-finish capacity and device assembly. New indication approvals can create demand faster than the supply capacity expands. Companies must invest before a therapy achieves its full commercial scale. Oral small-molecule therapies may use more conventional manufacturing infrastructure. That difference could influence the nature of competition after patent expiry. Product success will depend on clinical evidence, supply reliability, delivery format, and reimbursement. The cardiometabolic drugs market is exposed when a small number of platform molecules carry a large share of new value.
Complete Report Scope:
- By Therapeutic Area
- Diabetes
- Obesity & Weight Management
- Cardiovascular Diseases (Hypertension, Dyslipidemia, ASCVD, Stroke)
- Heart Failure & Cardiorenal Diseases
- Metabolic Liver Diseases (MASH/MASLD)
- By Drug Class
- GLP-1 & Incretin-Based Therapies
- SGLT2 Inhibitors
- Insulin & Traditional Antidiabetic Drugs
- Antihypertensive Drugs
- Lipid-Lowering Drugs
- Anticoagulants & Antiplatelet Drugs
- Other Cardiometabolic Drugs
- By Molecule / Product
- Semaglutide
- Tirzepatide
- Empagliflozin
- Dapagliflozin
- Atorvastatin/Rosuvastatin
- Apixaban/Rivaroxaban
- Other Products
- By Route of Administration
- Oral
- Injectable
- Other Routes
- By Formulation and Dosing Frequency
- Tablets & Capsules
- Prefilled Pens & Autoinjectors
- Vials & Cartridges
- Long-Acting Formulations
- By Patient Type
- Diabetes Patients
- Obesity Patients
- Cardiovascular Disease Patients
- Cardiorenal Disease Patients
- Metabolic Liver Disease Patients
- Pediatric & Geriatric Patients
- By Distribution Channel
- Hospital Pharmacies
- Retail Pharmacies
- Online Pharmacies
- Institutional & Direct Channels
- By Geography
- North America
- United States
- Canada
- Mexico
- Europe
- Germany
- United Kingdom
- France
- Italy
- Spain
- Rest of Europe
- Asia-Pacific
- China
- Japan
- India
- South Korea
- Australia
- Rest of Asia-Pacific
- Middle East and Africa
- GCC
- South Africa
- Rest of Middle East and Africa
- South America
- Brazil
- Argentina
- Rest of South America
- North America
Geography Analysis
North America held 41.3% of the cardiometabolic drugs market share in 2025. The United States combines high medicine prices, broad guideline use, and strong uptake of evidence-based therapies. GLP-1 and SGLT2 medicines benefit from established specialist networks and payer coverage for qualifying patients. Canada uses provincial formulary processes and health technology assessments to manage access. Mexico has a growing private-pay obesity treatment channel as distribution networks develop. U.S. payer management remains a restraint for high-cost medicines. The Inflation Reduction Act also creates a pricing consideration for Medicare and commercial plan benchmarks. North America remains important for branded revenue, even as access controls become stricter.
Europe is the second-largest geographic area for the cardiometabolic drugs market. Germany, the United Kingdom, France, Italy, and Spain account for much of the regional demand. Europe has a large disease burden but lower branded prices than North America. Reimbursement decisions commonly require health technology assessments and evidence of outcomes. Rezdiffra's European authorization in 2025 and UK authorization in 2026 expanded treatment options for MASH. Generic competition is also expected to place pressure on anticoagulant and SGLT2 inhibitor revenue. The region rewards clinical evidence but limits revenue through structured pricing and reimbursement processes.
Asia-Pacific is forecast to grow at a 12.2% CAGR through 2031, the highest geographic rate. China and India provide large diabetes populations and expanding pathways for new treatments. India's Abbott and Novo Nordisk collaboration illustrates the need for broad distribution systems. Japan combines extensive coverage with periodic pricing revisions. Middle East, Africa, and South America remain smaller but expanding areas. Urbanization and dietary change are increasing cardiometabolic risk across Saudi Arabia, South Africa, Brazil, and Argentina. High out-of-pocket costs and cold-chain requirements restrict injectable access outside major urban centers. These areas offer volume potential, but affordability and health-system capacity remain decisive.
List of Companies Covered in this Report:
- Novo Nordisk
- Eli Lilly and Company
- Sanofi
- AstraZeneca
- Boehringer Ingelheim
- Merck
- Bristol-Myers Squibb
- Pfizer
- Novartis
- Bayer
- Amgen
- Abbvie
- Roche
- Gilead Sciences
- Takeda Pharmaceuticals
- Biocon
- Biomarin Pharmaceutical
- Cipla
- Glenmark Pharmaceuticals
Additional Benefits:
- The market estimate (ME) sheet in Excel format
- 3 months of analyst support
TABLE OF CONTENTS
1 INTRODUCTION
- 1.1 Study Assumptions and Market Definition
- 1.2 Scope of the Study
2 RESEARCH METHODOLOGY
3 EXECUTIVE SUMMARY
4 MARKET LANDSCAPE
- 4.1 Market Overview
- 4.2 Market Drivers
- 4.2.1 Rising Cardiometabolic Disease Burden and Treatment Gaps
- 4.2.2 Multi-Indication Expansion of Incretin and SGLT2 Therapies
- 4.2.3 Earlier Risk-Reduction Treatment Enabled by Outcome Trials and Guidelines
- 4.2.4 Emerging-Market Diagnosis and Treatment-Coverage Expansion
- 4.2.5 Oral and Long-Acting Formats Reducing Administration Friction
- 4.2.6 Comorbidity-Linked Reimbursement and Real-World Evidence
- 4.3 Market Restraints
- 4.3.1 High Out-of-Pocket Costs and Payer Utilization Controls
- 4.3.2 Generic Erosion and Therapeutic Price Compression
- 4.3.3 Treatment Discontinuation from Tolerability and Persistence Friction
- 4.3.4 Counterfeit, Compounded and Gray-Market Product Risk
- 4.4 Supply-Chain Analysis
- 4.5 Regulatory Landscape
- 4.6 Technological Outlook
- 4.7 Porters Five Forces Analysis
- 4.7.1 Threat of New Entrants
- 4.7.2 Bargaining Power of Suppliers
- 4.7.3 Bargaining Power of Buyers
- 4.7.4 Threat of Substitutes
- 4.7.5 Competitive Rivalry
5 MARKET SIZE AND GROWTH FORECASTS
- 5.1 By Therapeutic Area
- 5.1.1 Diabetes
- 5.1.2 Obesity & Weight Management
- 5.1.3 Cardiovascular Diseases (Hypertension, Dyslipidemia, ASCVD, Stroke)
- 5.1.4 Heart Failure & Cardiorenal Diseases
- 5.1.5 Metabolic Liver Diseases (MASH/MASLD)
- 5.2 By Drug Class
- 5.2.1 GLP-1 & Incretin-Based Therapies
- 5.2.2 SGLT2 Inhibitors
- 5.2.3 Insulin & Traditional Antidiabetic Drugs
- 5.2.4 Antihypertensive Drugs
- 5.2.5 Lipid-Lowering Drugs
- 5.2.6 Anticoagulants & Antiplatelet Drugs
- 5.2.7 Other Cardiometabolic Drugs
- 5.3 By Molecule / Product
- 5.3.1 Semaglutide
- 5.3.2 Tirzepatide
- 5.3.3 Empagliflozin
- 5.3.4 Dapagliflozin
- 5.3.5 Atorvastatin/Rosuvastatin
- 5.3.6 Apixaban/Rivaroxaban
- 5.3.7 Other Products
- 5.4 By Route of Administration
- 5.4.1 Oral
- 5.4.2 Injectable
- 5.4.3 Other Routes
- 5.5 By Formulation and Dosing Frequency
- 5.5.1 Tablets & Capsules
- 5.5.2 Prefilled Pens & Autoinjectors
- 5.5.3 Vials & Cartridges
- 5.5.4 Long-Acting Formulations
- 5.6 By Patient Type
- 5.6.1 Diabetes Patients
- 5.6.2 Obesity Patients
- 5.6.3 Cardiovascular Disease Patients
- 5.6.4 Cardiorenal Disease Patients
- 5.6.5 Metabolic Liver Disease Patients
- 5.6.6 Pediatric & Geriatric Patients
- 5.7 By Distribution Channel
- 5.7.1 Hospital Pharmacies
- 5.7.2 Retail Pharmacies
- 5.7.3 Online Pharmacies
- 5.7.4 Institutional & Direct Channels
- 5.8 By Geography
- 5.8.1 North America
- 5.8.1.1 United States
- 5.8.1.2 Canada
- 5.8.1.3 Mexico
- 5.8.2 Europe
- 5.8.2.1 Germany
- 5.8.2.2 United Kingdom
- 5.8.2.3 France
- 5.8.2.4 Italy
- 5.8.2.5 Spain
- 5.8.2.6 Rest of Europe
- 5.8.3 Asia-Pacific
- 5.8.3.1 China
- 5.8.3.2 Japan
- 5.8.3.3 India
- 5.8.3.4 South Korea
- 5.8.3.5 Australia
- 5.8.3.6 Rest of Asia-Pacific
- 5.8.4 Middle East and Africa
- 5.8.4.1 GCC
- 5.8.4.2 South Africa
- 5.8.4.3 Rest of Middle East and Africa
- 5.8.5 South America
- 5.8.5.1 Brazil
- 5.8.5.2 Argentina
- 5.8.5.3 Rest of South America
- 5.8.1 North America
6 COMPETITIVE LANDSCAPE
- 6.1 Market Concentration
- 6.2 Market Share Analysis
- 6.3 Company Profiles (includes Global Level Overview, Market Level Overview, Core Segments, Financials as available, Strategic Information, Market Rank/Share, Products and Services, Recent Developments)
- 6.3.1 Novo Nordisk A/S
- 6.3.2 Eli Lilly and Company
- 6.3.3 Sanofi
- 6.3.4 AstraZeneca plc
- 6.3.5 Boehringer Ingelheim International GmbH
- 6.3.6 Merck & Co., Inc.
- 6.3.7 Bristol-Myers Squibb Company
- 6.3.8 Pfizer Inc.
- 6.3.9 Novartis AG
- 6.3.10 Bayer AG
- 6.3.11 Amgen Inc.
- 6.3.12 AbbVie Inc.
- 6.3.13 F. Hoffmann-La Roche Ltd
- 6.3.14 Gilead Sciences, Inc.
- 6.3.15 Takeda Pharmaceutical Company Limited
- 6.3.16 Biocon Limited
- 6.3.17 BioMarin Pharmaceutical Inc.
- 6.3.18 Cipla Limited
- 6.3.19 Glenmark Pharmaceuticals Limited
7 MARKET OPPORTUNITIES AND FUTURE OUTLOOK
- 7.1 White-Space and Unmet-Need Assessment


