

|
시장보고서
상품코드
2154461
하수체 기능 저하증 진단 : 시장 점유율 분석, 업계 동향과 통계, 성장 예측(2026-2031년)Hypopituitarism Diagnostics - Market Share Analysis, Industry Trends & Statistics, Growth Forecasts (2026 - 2031) |
||||||
 Mordor Intelligence
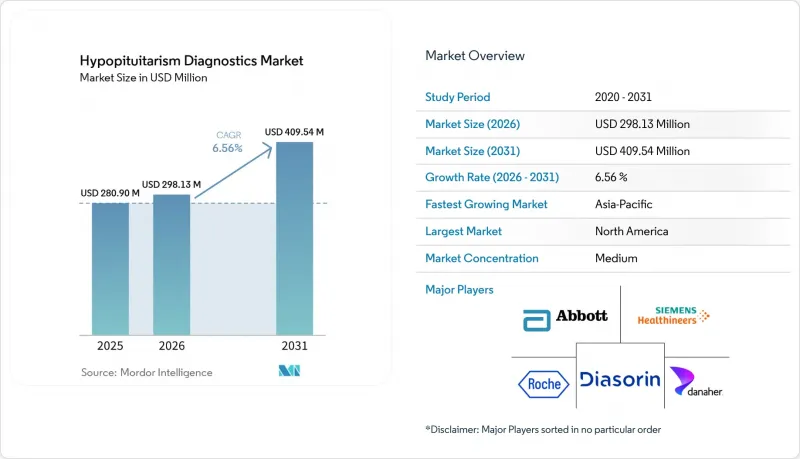
에 따르면 하수체 기능 저하증의 진단 시장은 2025년 2억 8,090만 달러, 2026년 2억 9,813만 달러에서 2031년까지 4억 954만 달러로 확대할 것으로 예측되고 있으며, 2026-2031년까지 연평균 성장률(CAGR)은 6.56%에 달할 전망입니다.
전 세계 뇌하수체 기능 저하증 진단 시장의 동향 및 인사이트
뇌하수체 호르몬 결핍증 진단 건수의 증가
뇌하수체 기능 저하증은 본질적으로 희귀 질환이라기보다는 진단이 간과되기 쉬운 질환으로, 그 결과 상당수의 환자가 확정 진단을 받지 못하고 적절한 호르몬 검사도 받지 못한 상황에 처해 있습니다. 성인의 유병률은 10만 명당 37.5-45.5건으로, 이는 뇌하수체 기능 저하증 진단 시장에 있으며, 중요한 환자층을 나타냅니다. 특히 치료를 받지 않을 경우 표준화 사망률이 일반 인구의 약 8배에 달한다는 점에서 그 중요성은 더욱 커집니다. 두통이나 신경학적 평가에서 MRI 활용이 증가함에 따라 비록 다른 임상적 우려를 이유로 영상 검사가 지시된 경우라 하더라도 생화학적 추적 관찰이 필요한 뇌하수체 우발성 종양이 확인되고 있습니다. 안부 종양 및 기타 점유성 병변은 후천성 사례의 약 50%를 차지하고 있으며, MRI의 활용이 더욱 광범위해지면 더 많은 환자를 조기에 평가 대상으로 삼을 수 있습니다. 정기적인 기초 호르몬 패널 검사를 통해 코르티솔, ACTH, TSH, 유리 T4, IGF-1 및 성선 자극 호르몬을 동시에 측정할 수 있으므로, 의뢰 경로 내에서 포괄적인 평가를 보다 실용적으로 수행할 수 있습니다.
외상성 뇌손상 및 방사선 치료 후 환자군에 대한 선별 검사 확대
외상성 뇌손상 및 방사선 관련 뇌하수체 기능 부전은 임상적으로 중요한 환자군이지만, 지금까지 초기 치료 후의 선별 검사는 일관성이 부족했습니다. 2024년 메타분석에 따르면 뇌·두경부 종양에 대한 방사선 치료를 받은 성인의 61%에서 어떤 형태의 뇌하수체 기능 부전이 확인되었으며, 그중에서도 성장호르몬 결핍증이 40%로 가장 많이 보고되었습니다. 임상적 추적 관찰 지침에 따르면 중등도에서 중증의 뇌 손상 후에는 체계적인 평가를 실시해야 하며, 증상이나 위험 요인이 남아 있는 경우 정해진 간격으로 검사를 실시하도록 되어 있습니다. 이러한 치료 경로를 통해 일회성 진단 기회가 아닌, 수년에 걸친 반복적인 검사가 이루어지게 됩니다. 따라서 뇌하수체 기능 저하증 진단 시장은 일관된 추적 관찰 경로를 통해 신경외상학, 종양학, 내분비학 및 검사 부서가 연계된 병원 시스템으로부터 혜택을 받고 있습니다.
기초 및 동적 호르몬 검사의 복잡한 해석
뇌하수체 기능 저하증 검사에서는 분석 전, 측정 중, 그리고 결과를 임상적 판단에 적용할 때 오류가 발생할 가능성이 있으므로 신중한 해석이 요구됩니다. 2024년 총설에서는 교차 반응, 간섭 항체, 영양 보충제와의 상호 작용, 그리고 표준화가 불충분한 분석 기준치가 검사 결과를 오도하는 반복적인 원인으로 지목되었습니다. 인슐린 내성 검사, 글루카곤 자극 검사 및 ACTH 자극 검사는 상당한 시간이 소요되며, 임상적 감독이 필요할 수 있습니다. 또한 이러한 검사 결과는 사용하는 분석 플랫폼이나 적용되는 기준치에 따라 변동하므로 검사실 간의 직접적인 비교가 제한됩니다. 이러한 복잡성으로 인해 뇌하수체 기능 저하증 진단 시장의 성장이 둔화되고 있습니다. 이는 검사실에 전문적인 프로토콜이 필요하고, 임상 팀이 확인을 요청할 가능성이 있으며, 전체 진단 과정에 더 많은 자원이 소요되기 때문입니다.
부문 분석
2025년, 호르몬 혈액 검사는 매출 점유율의 40.26%를 차지하며 뇌하수체 기능 저하증 진단 시장에서 가장 큰 검사 유형이 되었습니다. 임상의는 결핍증의 원인을 특정하기 전에 여러 뇌하수체 축을 평가해야 하므로, 일반적으로 기초 다호르몬 패널 검사가 첫 번째 단계가 됩니다. ECLIA 및 기타 자동 면역 분석법을 통해 병원 검사실에서는 이러한 측정을 일상적인 업무 흐름 속에서 처리할 수 있게 되었습니다.
기저 수치가 불분명하거나 성장호르몬 및 ACTH 결핍증 확인이 필요한 경우에는 동적 검사 및 자극 검사가 다음 단계가 됩니다. 인슐린 내성 검사, 글루카곤 자극 검사, ACTH 자극 검사의 프로토콜에는 감독 하에 채혈이 필요하므로 이러한 검사는 여전히 병원이나 전문 시설에 집중되어 있습니다. 영상 진단은 구조적 질환이 의심되는 경우나 치료 관련 뇌하수체염에서 뇌하수체 MRI의 활용에 힘입어, 2031년까지 연평균 성장률(CAGR) 7.16%로 성장할 것으로 예측됩니다. 뇌하수체 미세선종이나 구조적 변화를 고해상도로 탐지하기 위한 AI 지원형 MRI 기법이 검토되고 있으며, 이를 통해 복잡한 검사 과정에서 영상 진단의 역할이 강화될 가능성이 있습니다.
2025년 매출에서 임상 진단이 차지하는 비중은 44.32%로, 뇌하수체 기능 저하증 진단 시장에서 증상에 기반한 의뢰가 여전히 중요한 역할을 하고 있음을 반영합니다. 피로, 성선 기능 저하증, 성장 장애, 시각 증상 및 기타 내분비계 문제가 임상 의사의 초기 검사 의뢰로 이어지는 경우가 많습니다. 따라서 임상 진단은 앞으로도 병원 내분비과 및 전문 진료 서비스 전반에 걸쳐 주요 검사 기반을 계속 제공할 것입니다.
스크리닝 시장은 2031년까지 연평균 성장률(CAGR) 8.24%로 성장할 것으로 예상되며, 가장 빠르게 성장하는 응용 분야가 될 전망입니다. 외상성 뇌손상, 두부 방사선 치료, 체크포인트 억제제 치료에 대한 체계적인 경과 관찰을 통해 정기적인 간격으로 평가 가능한 알려진 위험군이 형성됩니다. 호르몬 대체요법을 받고 있는 환자의 경우, 치료의 적절성을 평가하기 위해 정기적인 검사가 필요하므로 모니터링은 계속해서 안정적인 용도로 자리매김할 것입니다.
지역별 분석
북미는 2025년에 매출 점유율의 46.31%를 차지하며, 뇌하수체 기능 저하증 진단 시장에서 가장 큰 지역 점유율을 확립했습니다. 미국에는 메이요 클리닉, 배로 신경학 연구소, 존스 홉킨스 대학교 등 학술 의료 기관에 뇌하수체 전문 센터가 집중되어 있으며, 이들 센터는 고도로 복잡한 검사 및 다학제적 의뢰를 지원하고 있습니다. 캐나다에서는 뇌 손상 치료와 내분비학적 추적 관찰 간의 연계를 공식적으로 확립해 가는 주(州)의 의료제도를 통해 검사 건수가 증가하고 있습니다. 또한 이 지역에는 로슈, 지멘스 헬스인어즈, 애보트사의 면역측정 플랫폼이 널리 도입되어 있으며, 일상적인 내분비 검사 처리 능력을 지원하고 있습니다.
유럽은 두 번째로 큰 지역 블록으로, 독일, 영국, 프랑스, 이탈리아, 스페인에 있는 성숙한 전문의 네트워크와 국립 표준 검사 기관에 의해 지원되고 있습니다. 유럽연합(EU)의 체외진단용 의료기기 규정에 따라 검증 요건이 변경됨에 따라 강력한 규제 관련 문서를 갖춘 확립된 플랫폼이 유리할 가능성이 있습니다. 체계화된 뇌 손상 경과 관찰 및 내분비과로의 의뢰 체계는 전문의 수용 체계가 잘 갖춰진 지역에서 동적 검사에 대한 수요를 지원하고 있습니다. 독일, 프랑스, 이탈리아, 스페인 및 영국에서는 3차 의료 경로 내에서 복잡한 의뢰 사례를 처리할 수 있는 내분비학 네트워크가 확립되어 있습니다. 폴란드와 체코 공화국을 포함한 동유럽 국가들에서는 전문적인 검사에 대한 수요가 증가하고 있지만, 첨단 플랫폼의 조달 주기로 인해 단기적인 도입이 지연될 가능성이 있습니다. 이러한 차이로 인해 지역별 뇌하수체 기능 저하증 진단 시장에서 기회는 제각각입니다.
아시아태평양은 2031년까지 연평균 성장률(CAGR) 9.23%로 성장할 것으로 예측되며, 뇌하수체 기능 저하증 진단 시장 규모 측면에서 지역별 가장 높은 성장률을 보이고 있습니다. 의료 인프라에 대한 투자, 전문의 양성 확대, 그리고 내분비 질환에 대한 의식의 향상가 중국, 인도, 일본, 한국에서의 도입을 지원하고 있습니다. 일본에서는 전엽 뇌하수체 기능 저하증이 ‘지정 난치성 질환’으로 지정되어 있으며, 이에 따라 진단 검사가 보험 적용 대상이 되며, 공표된 기준에 따른 다축 호르몬 평가가 의무화되어 있습니다. 중국에서는 병원을 통한 일원화된 조달 체계와 화학발광 면역측정법의 활용 확대가 호재로 작용하고 있습니다. 인도와 한국에서는 도시 지역의 3차 의료기관에서 내분비 의료 서비스가 확대되고 있으나, 이러한 지역 이외에서는 여전히 접근성에 편차가 나타나고 있습니다. 남미, 중동 및 아프리카에서는 브라질과 사우디아라비아를 주요 거점으로 하여 낮은 수준에서 도입이 진행되고 있습니다. 그러나 전문의 수가 제한적이고 검사 인프라가 분산되어 있으며, 이들 지역에서의 도입은 여전히 더딘 상황입니다.
기타 혜택:
- 엑셀 형식의 시장 예측(ME) 시트
- 3개월간의 애널리스트 지원
목차
제1장 서론
- 조사 전제조건과 시장 정의
- 조사 범위
제2장 조사 방법
제3장 개요
제4장 시장 구도
- 시장 개요
- 시장 성장 촉진요인
- 시장 성장 억제요인
- 공급/밸류체인 분석
- 규제 상황
- 기술 전망
- Porter's Five Forces 분석
제5장 시장 규모와 성장 예측
- 테스트 유형별
- 용도별
- 기술별
- 최종사용자별
- 지역별
- 북미
- 미국
- 캐나다
- 멕시코
- 유럽
- 독일
- 영국
- 프랑스
- 이탈리아
- 스페인
- 기타 유럽 국가
- 아시아태평양
- 중국
- 일본
- 인도
- 호주
- 한국
- 기타 아시아태평양 국가
- 중동 및 아프리카
- GCC
- 남아프리카공화국
- 기타 중동 및 아프리카 국가
- 남미
- 브라질
- 아르헨티나
- 기타 남미 국가
- 북미
제6장 경쟁 구도
- 시장 집중도
- 시장 점유율 분석
- 기업 개요
- Abbott Laboratories
- ARUP Laboratories
- Beckman Coulter, Inc.
- bioMerieux SA
- Bio-Rad Laboratories, Inc.
- Danaher Corporation
- DiaSorin S.p.A.
- F. Hoffmann-La Roche Ltd
- Fujirebio Holdings, Inc.
- Hologic, Inc.
- Immunodiagnostic Systems Holdings PLC
- Laboratory Corporation of America Holdings
- Mayo Clinic Laboratories
- Mindray Medical International Limited
- QIAGEN N.V.
- Quest Diagnostics Incorporated
- Revvity, Inc.
- Siemens Healthineers AG
- Thermo Fisher Scientific Inc.
- Tosoh Corporation
제7장 시장 기회와 향후 전망
KSAAccording to Mordor Intelligence, the hypopituitarism diagnostics market is projected to expand from USD 280.90 million in 2025 and USD 298.13 million in 2026 to USD 409.54 million by 2031, registering a CAGR of 6.56% between 2026 and 2031.
Global Hypopituitarism Diagnostics Market Trends and Insights
Rising Identification of Pituitary Hormone Deficiencies
Hypopituitarism is often missed rather than inherently rare, which leaves a substantial group of patients without a confirmed diagnosis or an appropriate hormone workup. Adult prevalence of 37.5 to 45.5 cases per 100,000 people indicates a meaningful pool for the hypopituitarism diagnostics market, especially because untreated disease carries a standardized mortality rate nearly 8 times that of the general population. Increased use of MRI for headaches and neurological assessment also identifies pituitary incidentalomas that require biochemical follow-up, even when imaging was ordered for a separate clinical concern. Sellar tumors and other space-occupying lesions account for nearly 50% of acquired cases, so broader MRI availability can bring more patients into assessment earlier. Routine basal panels can measure cortisol, ACTH, TSH, free T4, IGF-1, and gonadotropins together, which makes comprehensive evaluation more practical within referral pathways.
Expanding Screening of Traumatic Brain Injury and Post-Radiation Populations
Traumatic brain injury and radiation-related pituitary insufficiency represent clinically significant groups that have historically received inconsistent screening after the initial episode of care. A 2024 meta-analysis found any pituitary insufficiency in 61% of adults treated with radiation for brain, head, and neck tumors, with growth hormone deficiency reported most often at 40%. Clinical follow-up guidance calls for structured assessment after moderate to severe brain injury, with testing at defined intervals when symptoms or risk factors remain present. These care pathways create repeat testing over several years instead of a single diagnostic encounter. The hypopituitarism diagnostics market therefore gains from hospital systems that connect neurotrauma, oncology, endocrinology, and laboratory services through a consistent follow-up pathway.
Complex Interpretation of Basal and Dynamic Hormone Tests
Hypopituitarism testing requires careful interpretation because errors can arise before analysis, during measurement, and when results are applied to a clinical decision. A 2024 review identified cross-reactions, interfering antibodies, nutritional supplement interactions, and poorly standardized analytical cutoffs as recurring causes of misleading laboratory results. Insulin tolerance, glucagon stimulation, and ACTH stimulation testing can take considerable time and require clinical supervision. Their results also vary with the assay platform and cutoff applied, limiting direct comparison across laboratories. This complexity slows the hypopituitarism diagnostics market because laboratories need specialized protocols, clinical teams may seek confirmation, and the total diagnostic episode becomes more resource intensive.
Other drivers and restraints analyzed in the detailed report include:
- Growth of Automated Hormone Immunoassay and Pituitary Imaging Workflows
- Improved Detection of Immune Checkpoint Inhibitor-Associated Hypophysitis
- Limited Endocrinology Expertise Outside Specialist Centers
For complete list of drivers and restraints, kindly check the Table Of Contents.
Segment Analysis
Hormone blood tests held 40.26% revenue share in 2025, making them the largest test type in the hypopituitarism diagnostics market. Basal multi-hormone panels are usually the first step because clinicians need to evaluate several pituitary axes before confirming the source of a deficiency. ECLIA and other automated immunoassay methods allow hospital laboratories to process those measurements within routine workflows.
Dynamic and stimulation tests form the next layer when basal values are unclear or when confirmation of growth hormone and ACTH deficiency is needed. Insulin tolerance, glucagon stimulation, and ACTH stimulation protocols require supervised sampling, so they remain concentrated in hospitals and specialist centers. Imaging diagnostics is forecasted to grow at a 7.16% CAGR through 2031, supported by pituitary MRI use in suspected structural disease and treatment-related hypophysitis. AI-assisted MRI methods are being examined for higher-resolution detection of pituitary microadenomas and structural change, which can strengthen the role of imaging in complex workups.
Clinical diagnosis represented 44.32% of revenue in 2025, reflecting the continued role of symptom-led referrals in the hypopituitarism diagnostics market. Fatigue, hypogonadism, growth failure, visual symptoms, and other endocrine concerns often lead clinicians to request initial testing. Clinical diagnosis will therefore continue to supply the main testing base across hospital endocrinology and specialist services.
Screening is expected to grow at a 8.24% CAGR through 2031, making it the fastest-growing application. Structured follow-up for traumatic brain injury, cranial radiation, and checkpoint inhibitor treatment creates known at-risk groups that can be assessed on scheduled intervals. Monitoring remains a steady application for people receiving hormone replacement therapy, because periodic testing is needed to evaluate treatment adequacy.
Complete Report Scope:
- By Test Type
- Hormone Blood Tests
- Dynamic/Stimulation Tests
- Imaging Diagnostics
- Other Test Types
- By Application
- Clinical Diagnosis
- Screening
- Monitoring
- By Technology
- Immunoassay
- Molecular Diagnostics
- Imaging Technology
- By End-User
- Hospitals
- Diagnostic Laboratories
- Specialty Endocrinology Clinics
- Other End-Users
- By Geography
- North America
- United States
- Canada
- Mexico
- Europe
- Germany
- United Kingdom
- France
- Italy
- Spain
- Rest of Europe
- Asia-Pacific
- China
- Japan
- India
- Australia
- South Korea
- Rest of Asia-Pacific
- Middle East and Africa
- GCC
- South Africa
- Rest of Middle East and Africa
- South America
- Brazil
- Argentina
- Rest of South America
- North America
Geography Analysis
North America held 46.31% revenue share in 2025, giving it the largest regional position in the hypopituitarism diagnostics market. The United States has concentrated pituitary centers at academic medical institutions, including Mayo Clinic, Barrow Neurological Institute, and Johns Hopkins, which support high-complexity testing and multidisciplinary referrals. Canada adds volume through provincial healthcare systems that are formalizing links between brain injury care and endocrinology follow-up. The region also has a dense installed base of immunoassay platforms from Roche, Siemens Healthineers, and Abbott, which supports routine endocrine workflow capacity.
Europe is the second-largest regional block, supported by mature specialist networks and national reference laboratories in Germany, the United Kingdom, France, Italy, and Spain. The European Union In Vitro Diagnostics Regulation is changing validation requirements and can favor established platforms that have strong regulatory documentation. Structured brain injury follow-up and endocrine referral practices support demand for dynamic testing where specialist capacity is available. Germany, France, Italy, Spain, and the United Kingdom have established endocrinology networks that can process complex referrals within tertiary care pathways. Eastern European countries, including Poland and the Czech Republic, show growing need for specialized testing, although procurement cycles for advanced platforms can delay near-term uptake. These differences create a mixed opportunity across the regional hypopituitarism diagnostics market.
Asia-Pacific is projected to grow at a 9.23% CAGR through 2031, the fastest regional rate in the hypopituitarism diagnostics market size. Healthcare infrastructure investment, increasing specialist training, and wider awareness of endocrine disorders are supporting adoption in China, India, Japan, and South Korea. Japan classifies anterior pituitary hypofunction as a designated intractable disease, which provides insurance coverage for diagnostic workups and requires multi-axis hormone evaluation under published criteria. China benefits from centralized hospital procurement and increasing use of chemiluminescent immunoassay systems. India and South Korea are expanding endocrine services in urban tertiary centers, although access remains uneven beyond those locations. South America, the Middle East, and Africa are growing from a lower base, with Brazil and Saudi Arabia as key access points. Limited specialist density and fragmented laboratory infrastructure continue to slow adoption in these regions.
- Abbott Laboratories
- ARUP Laboratories
- Beckton Dickinson
- bioMerieux
- Bio-Rad Laboratories
- Danaher
- DiaSorin
- Roche
- Fujirebio Holdings, Inc.
- Hologic
- Immunodiagnostic Systems Holdings PLC
- LabCorp
- Mayo Clinic Laboratories
- Mindray
- QIAGEN
- Quest Diagnostics
- Revvity, Inc.
- Siemens Healthineers
- Thermo Fisher Scientific
- Tosoh
Additional Benefits:
- The market estimate (ME) sheet in Excel format
- 3 months of analyst support
TABLE OF CONTENTS
1 Introduction
- 1.1 Study Assumptions and Market Definition
- 1.2 Scope of the Study
2 Research Methodology
3 Executive Summary
4 Market Landscape
- 4.1 Market Overview
- 4.2 Market Drivers
- 4.2.1 Rising Identification of Pituitary Hormone Deficiencies
- 4.2.2 Increasing Testing of Patients with Pituitary Tumors and Treatment-Related Dysfunction
- 4.2.3 Expanding Screening of Traumatic Brain Injury and Post-Radiation Populations
- 4.2.4 Growth of Automated Hormone Immunoassay and Pituitary Imaging Workflows
- 4.2.5 Improved Detection of Immune Checkpoint Inhibitor-Associated Hypophysitis
- 4.2.6 Increasing Use of Copeptin and Multiplex Endocrine Testing in Ambiguous Cases
- 4.3 Market Restraints
- 4.3.1 Complex Interpretation of Basal and Dynamic Hormone Tests
- 4.3.2 Limited Endocrinology Expertise Outside Specialist Centers
- 4.3.3 Interassay Variability and Hormone Replacement Interference
- 4.3.4 Fragmented Adoption of Copeptin and Advanced Dynamic Testing
- 4.4 Supply/Value Chain Analysis
- 4.5 Regulatory Landscape
- 4.6 Technological Outlook
- 4.7 Porter's Five Forces Analysis
- 4.7.1 Threat of New Entrants
- 4.7.2 Bargaining Power of Suppliers
- 4.7.3 Bargaining Power of Buyers
- 4.7.4 Threat of Substitutes
- 4.7.5 Competitive Rivalry
5 Market Size & Growth Forecasts (Value, USD)
- 5.1 By Test Type
- 5.1.1 Hormone Blood Tests
- 5.1.2 Dynamic/Stimulation Tests
- 5.1.3 Imaging Diagnostics
- 5.1.4 Other Test Types
- 5.2 By Application
- 5.2.1 Clinical Diagnosis
- 5.2.2 Screening
- 5.2.3 Monitoring
- 5.3 By Technology
- 5.3.1 Immunoassay
- 5.3.2 Molecular Diagnostics
- 5.3.3 Imaging Technology
- 5.4 By End-User
- 5.4.1 Hospitals
- 5.4.2 Diagnostic Laboratories
- 5.4.3 Specialty Endocrinology Clinics
- 5.4.4 Other End-Users
- 5.5 By Geography
- 5.5.1 North America
- 5.5.1.1 United States
- 5.5.1.2 Canada
- 5.5.1.3 Mexico
- 5.5.2 Europe
- 5.5.2.1 Germany
- 5.5.2.2 United Kingdom
- 5.5.2.3 France
- 5.5.2.4 Italy
- 5.5.2.5 Spain
- 5.5.2.6 Rest of Europe
- 5.5.3 Asia-Pacific
- 5.5.3.1 China
- 5.5.3.2 Japan
- 5.5.3.3 India
- 5.5.3.4 Australia
- 5.5.3.5 South Korea
- 5.5.3.6 Rest of Asia-Pacific
- 5.5.4 Middle East and Africa
- 5.5.4.1 GCC
- 5.5.4.2 South Africa
- 5.5.4.3 Rest of Middle East and Africa
- 5.5.5 South America
- 5.5.5.1 Brazil
- 5.5.5.2 Argentina
- 5.5.5.3 Rest of South America
- 5.5.1 North America
6 Competitive Landscape
- 6.1 Market Concentration
- 6.2 Market Share Analysis
- 6.3 Company Profiles (includes Global level Overview, Market level overview, Core Segments, Financials as available, Strategic Information, Market Rank/Share for key companies, Products & Services, Recent Developments)
- 6.3.1 Abbott Laboratories
- 6.3.2 ARUP Laboratories
- 6.3.3 Beckman Coulter, Inc.
- 6.3.4 bioMerieux SA
- 6.3.5 Bio-Rad Laboratories, Inc.
- 6.3.6 Danaher Corporation
- 6.3.7 DiaSorin S.p.A.
- 6.3.8 F. Hoffmann-La Roche Ltd
- 6.3.9 Fujirebio Holdings, Inc.
- 6.3.10 Hologic, Inc.
- 6.3.11 Immunodiagnostic Systems Holdings PLC
- 6.3.12 Laboratory Corporation of America Holdings
- 6.3.13 Mayo Clinic Laboratories
- 6.3.14 Mindray Medical International Limited
- 6.3.15 QIAGEN N.V.
- 6.3.16 Quest Diagnostics Incorporated
- 6.3.17 Revvity, Inc.
- 6.3.18 Siemens Healthineers AG
- 6.3.19 Thermo Fisher Scientific Inc.
- 6.3.20 Tosoh Corporation
7 Market Opportunities & Future Outlook
- 7.1 White-space & Unmet-need Assessment


